
Hyaluronic acid in the glabella: why it is a high-risk area

 BeforeSimulation
- Artery
Quick facts
- Area
- The space between the eyebrows, over the root of the nose.
- Risk classification
- High vascular risk, listed among the areas most associated with visual complications.
- Common concern
- Vertical lines between the eyebrows (frown lines) and a static furrow.
- Usual first approach
- Treat the muscular component, generally with botulinum toxin, before considering a gel.
The glabella is the smooth space between the eyebrows, just above the root of the nose. It is also one of the areas where orofacial harmonization calls for the most caution with hyaluronic acid. The reason is not the aesthetic result but the vascular supply: fine vessels in this area connect with the circulation of the orbit, and a vascular occlusion there can have serious consequences, including vision loss.
This page is not an injection protocol. It lays out the risk reasoning, the alternatives to direct injection and what to prepare. Techniques and products are decisions for the licensed professional, according to the rules of their professional council in Brazil.
Why is the glabella a high-risk area?
The supratrochlear and supraorbital arteries run through the area. They are terminal branches of the circulation that starts at the ophthalmic artery. The dorsal nasal artery also connects to the orbital system. These connections, the anastomoses, allow material injected into one vessel to reach distant territories, in a retrograde direction, under pressure.
The ophthalmic artery gives rise to the central retinal artery. If a gel embolus reaches it, the retina is deprived of oxygen within minutes. For the mechanism, see visual complication after filler and vascular anastomoses of the face.
There is also skin risk. When the occlusion happens in smaller vessels, the skin of the glabella and the nasal root can become pale, painful and mottled, and progress to necrosis. Read glabellar vascular occlusion to learn how to recognize it.
What usually prompts the request?
The patient asks to "remove the angry line" or the vertical furrow between the eyebrows. These lines have two components that add up:
- Dynamic: contraction of the corrugator and the procerus, which furrow the brow.
- Static: a mark that stays at rest, from loss of elasticity and repeated folding of the skin.
Telling the two apart changes the approach. The page botulinum toxin in the glabellar complex covers the muscular approach, and the area is described in glabella.
| Component | Sign on examination | General direction |
|---|---|---|
| Dynamic | Line appears only when frowning | Muscle treatment is usually the first line |
| Mixed | Faint line at rest, deepens when frowning | Treat the muscle and reassess what remains |
| Deep static | Furrow visible at rest and when the skin is stretched | Assess alternatives to direct injection; risk and benefit discussion |
When does hyaluronic acid enter the conversation?
Some professionals use gel in a very restricted way in the glabella, for a residual static furrow after the muscle has been controlled, and with specific training in vascular anatomy and complication management. Others decide never to inject the area. Both positions are defensible; what is not defensible is recommending it without assessing the risk with the patient.
The useful question is not "can it be done?" but "does the expected benefit justify the risk the patient is accepting, and do I know how to manage it if something goes wrong?". If the answer is doubtful, lower the ambition of the plan.
What are the alternatives to direct injection in the glabella?
When the goal is to soften the frown lines, there are paths that do not place gel in the risk territory. They vary by cause, and the choice is clinical:
- treat the muscular component with botulinum toxin, which reduces the force that folds the skin;
- skin quality approaches in a superficial layer, such as those discussed in skinbooster and microneedling with biostimulator or HA;
- sun protection and a dermatological routine, which act on photoaging;
- treat the forehead and the eyebrow as a set, because frowning and lifting compensate for each other (see botulinum toxin in the frontalis muscle).
Each alternative has its own indications and limits, and none is free of risk. The point is that there are options with less exposure than gel at a vascular plane.
What should be prepared if the decision is to treat?
For the professional who decides to inject the glabella, preparation is part of the procedure, not a detail:
The safety time-out before injecting helps review this set at the right moment.
How to recognize a complication?
The signs call for attention during and right after the procedure. The practical literature describes intense, disproportionate pain, blanching of the skin (sometimes in a branching pattern), color change, a burning sensation and, in the ocular forms, sudden loss or blurring of vision, eye pain, diplopia or a drooping eyelid.
More details in visual complication after filler, hyaluronidase in the clinic and recording the complication in the patient record.
Myths and facts about the glabella
How does Harmy fit into this conversation?
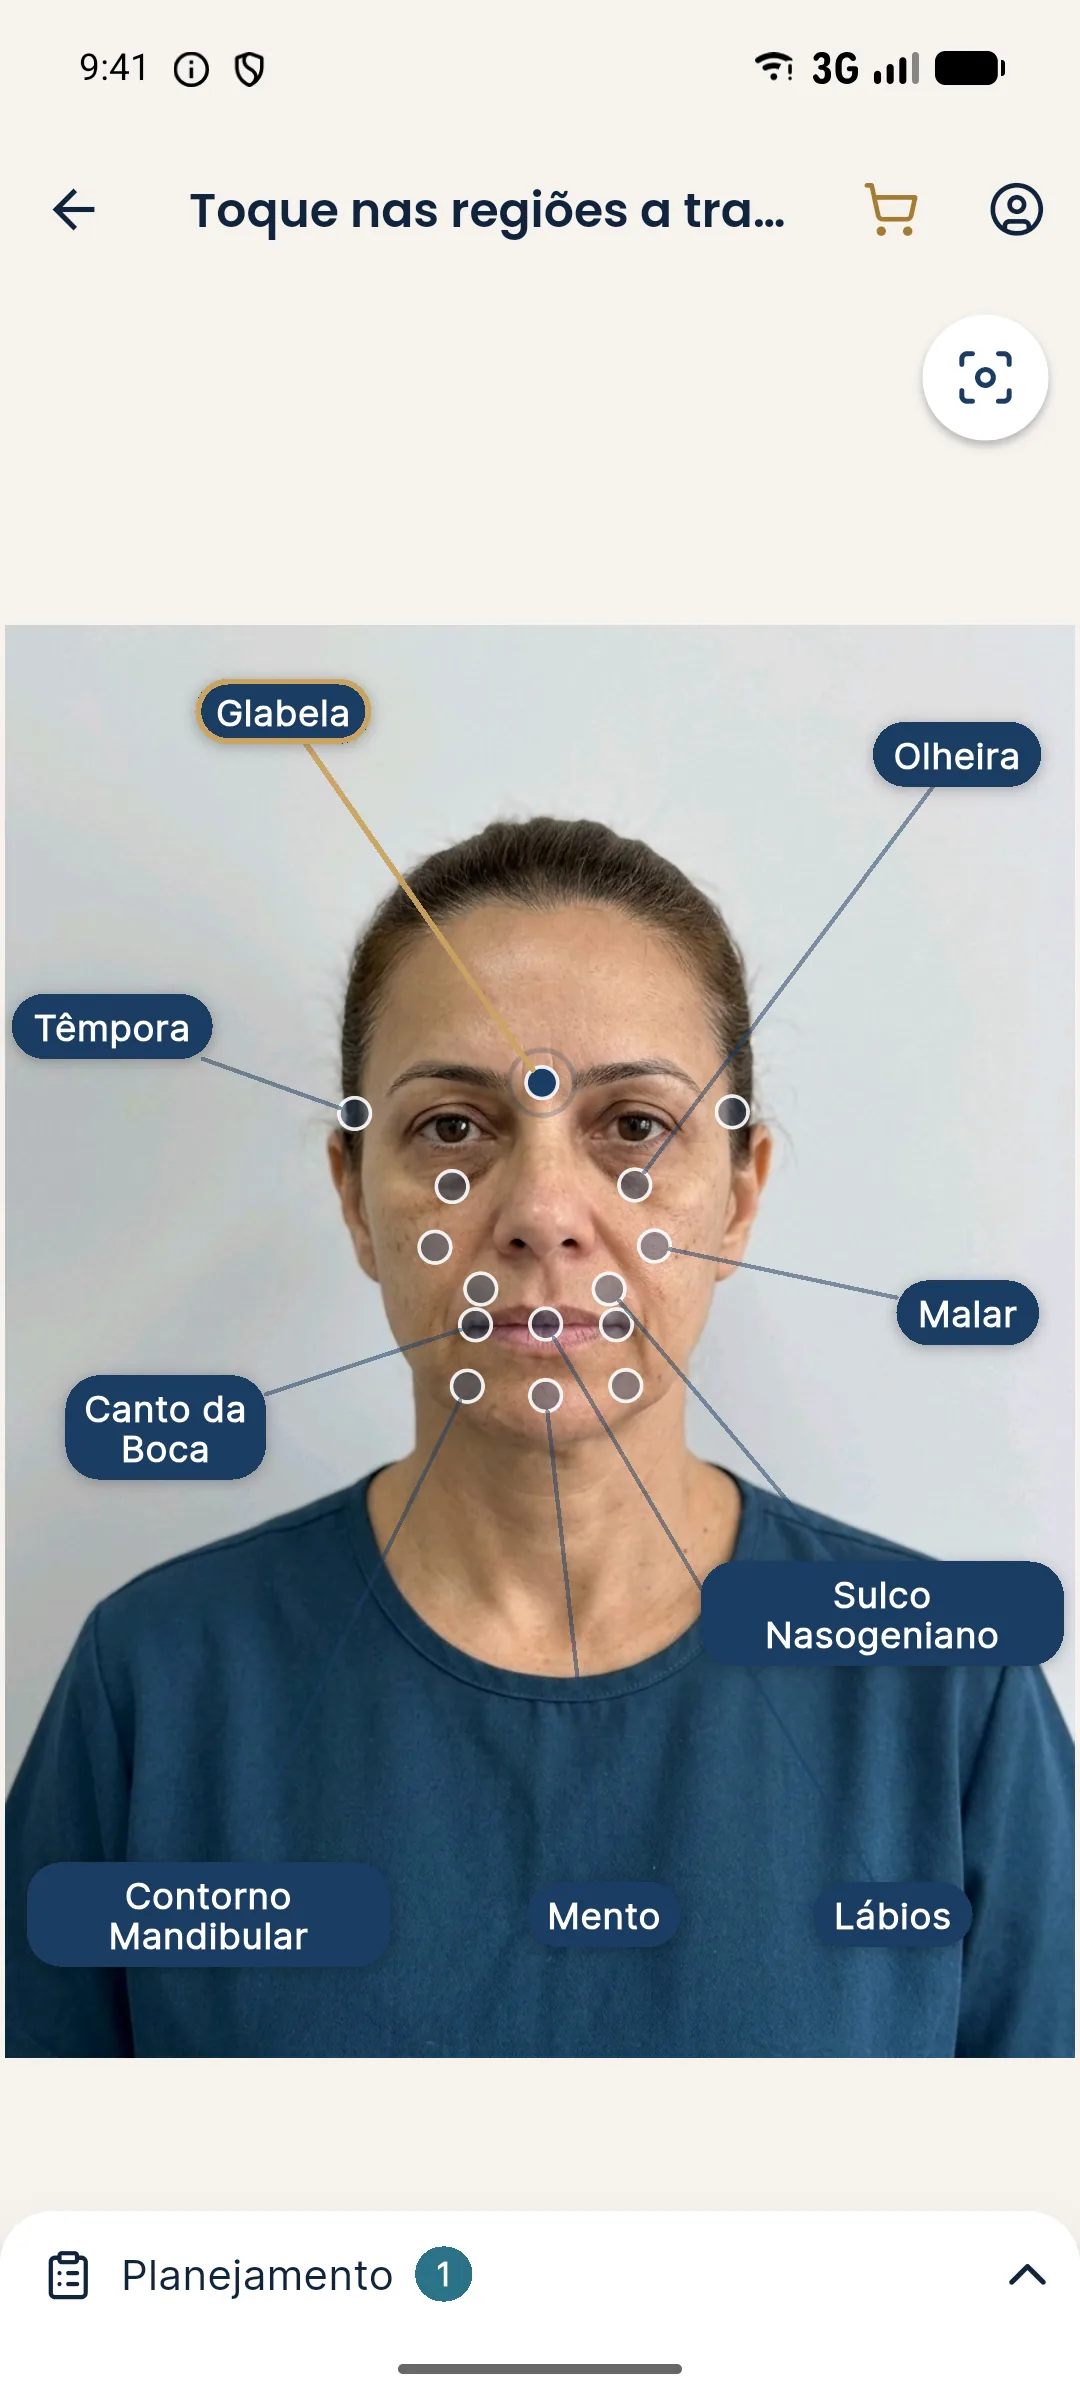
In the app, Glabella is one of the marking points. The projection helps show the patient the expected effect of an approach to frown lines and align expectations, without interfering with the choice of technique. The volume of the Glabella point in the app is a symbolic unit, not a dosing instruction.
What to remember
The glabella combines high perceived benefit for the patient with high vascular risk. Recognizing the muscular component, offering alternatives, stating the risk explicitly in the consent, keeping hyaluronidase and urgent referral routes ready and recording everything is what separates a responsible decision from a habitual indication. For the overall picture, see vascular danger zones of the face and safety and complications. For a region-by-region reading of gel use, see hyaluronic acid by area.
Frequently asked questions
Can hyaluronic acid filler be used in the glabella?
It is described, but the glabella is among the areas with the highest vascular risk, and many professionals avoid direct injection or reserve it for selected cases and specifically trained practitioners. The decision rests with the licensed professional, after assessment and consent.
Why is the glabella so dangerous?
Because vessels such as the supratrochlear artery communicate with the circulation of the orbit, and an occlusion there can compromise the retina or the skin. Anastomoses vary from person to person, which makes the risk unpredictable.
What is the alternative to filler in the glabella?
When the problem is muscular, the muscle is usually treated, and for the static furrow there are strategies that avoid direct injection, such as skin care and superficial approaches. The choice depends on the cause and on the professional.
What should be done if a visual complication is suspected?
Stop the procedure, activate the emergency protocol and refer urgently to ophthalmology care. Do not wait to see how it evolves before deciding.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.