
Nasal Anatomy for Injectables
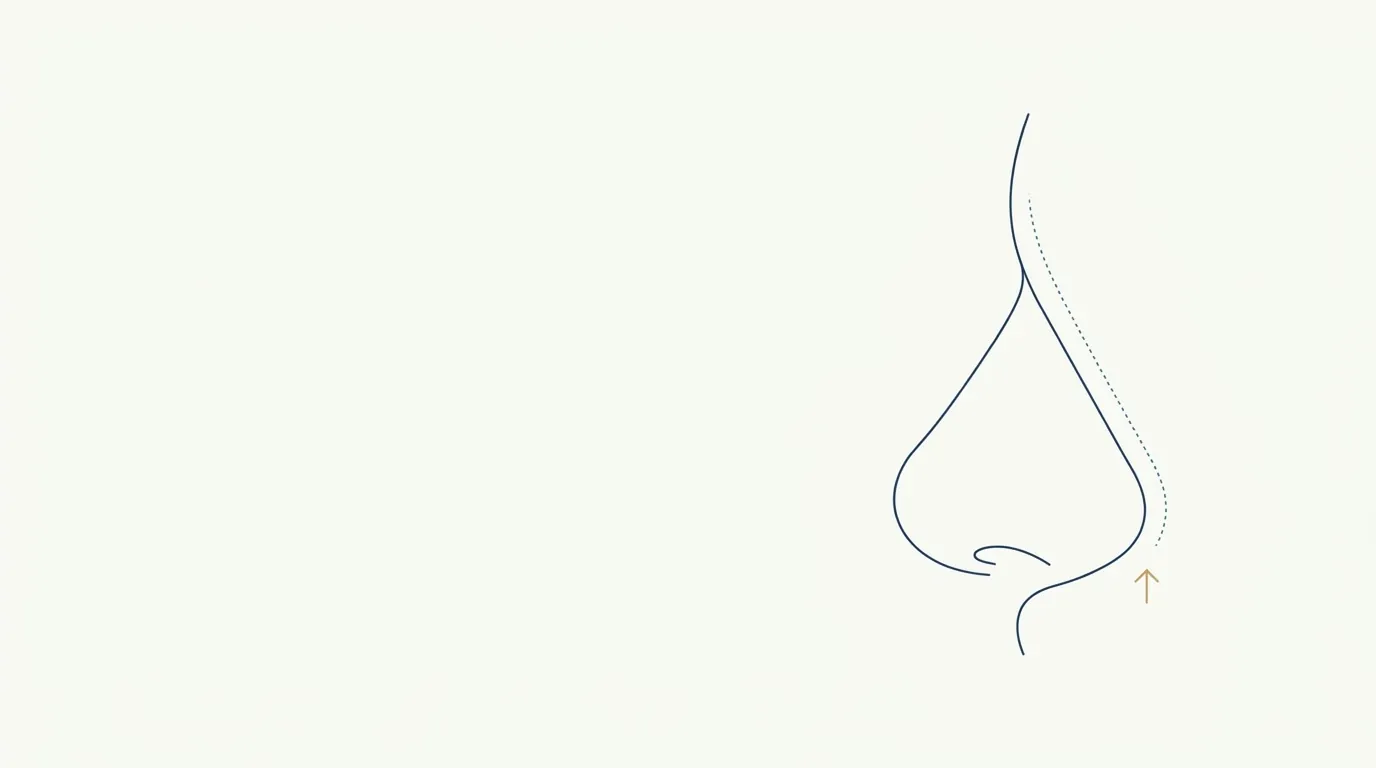
- Highlighted area
Quick facts
- Structure
- Osteocartilaginous pyramid: bony upper third, cartilaginous middle and lower thirds, covered by skin of variable thickness.
- Blood supply
- Branches of the facial artery (via the angular and lateral nasal arteries) and of the ophthalmic system (dorsal nasal artery), with anastomoses between the two systems.
- Skin
- Thin over the dorsum and thicker and more sebaceous at the tip and alae; it affects the risk of irregularities and how visible the product is.
- Main risk
- Vascular occlusion with skin necrosis and, more rarely, visual compromise, in an area with little tissue margin.
The nose is one of the most requested and most delicate areas of the face. It sits at the center of the face, defines how the profile reads and combines thin skin, cartilaginous structure and a blood supply connected to the eye, which is a rare mix. Anyone assessing injectables in this area needs to know the anatomy at a level that the patient's request ("just lift the tip") does not reveal. This guide reviews the structure, vessels, nerves and danger zones, and relates them to the indication. Technique, plan, volume and product choice are decisions for the qualified professional, following the label and the rules of their professional council.
How is the nose built?
Think of three layers: skeleton, soft tissue and skin.
Osteocartilaginous skeleton
- Upper third: formed by the nasal bones, the bony portion of the pyramid. It is rigid and relatively immobile.
- Middle third: formed by the upper lateral cartilages, which meet the septum at the midline. It has some mobility.
- Lower third (tip and alae): formed by the alar cartilages, which define the tip, the nostrils and nasal mobility. See nasal cartilages.
The piriform aperture of the maxilla forms the bony base of the pyramid and supports the whole structure.
Soft tissue
Over the skeleton lie small nasal muscles, a fibrofatty layer and the aponeurotic system of the face. The thickness of these layers varies widely along the dorsum, tip and alae, and from patient to patient.
Skin
The skin is thin and mobile over the dorsum, and thicker and more sebaceous at the tip and alae. Its thickness determines how much of the skeletal relief shows, how much the skin "hides" irregularities and how visible a product is beneath it.
Blood supply: what explains the risk
The nasal blood supply is the reason this area gets so much attention in safety discussions. It comes from two systems:
- Facial artery system: gives rise to the angular artery, which runs along the side of the nose and connects with branches of the ophthalmic system, and to the lateral nasal artery, which supplies the ala and the lateral dorsum.
- Ophthalmic artery system: gives off the dorsal nasal artery, which runs down the dorsum and anastomoses with branches of the facial artery.
- Columellar artery: supplies the columella and the tip, arising from labial branches.
Because the two systems communicate, an embolism can lead to damage to the nasal skin and, in rare cases, to the retina. An in-depth explanation is in vascular anastomoses of the face, and the clinical picture is described in nasal vascular occlusion.
Nerves and sensation
Sensation in the nose comes from branches of the trigeminal nerve. The dorsum and tip are supplied by branches of the ophthalmic division, while the alae and the lateral portion receive branches of the maxillary division, especially the infraorbital nerve. Understanding the distribution is useful for planning patient comfort, assessing changes in sensation and recognizing atypical signs after the procedure. See trigeminal nerve and infraorbital nerve.
Angles and proportions the patient wants to change
The complaint is almost never "I want more volume in the middle third." It is a reading of the profile or the front view, and anatomy translates it into measurements.
| Measurement or angle | What it describes | Why it matters in the assessment |
|---|---|---|
| Nasofrontal angle | Transition between the forehead and the dorsum | Defines the depth of the nasal root |
| Nasofacial angle | Slope of the dorsum relative to the facial plane | Relates the nose to the profile |
| Nasolabial angle | Between the columella and the upper lip | Assesses tip rotation |
| Base width | Distance between the alae | Balance with the width of the face |
| Tip projection | How far the tip projects | Perceived balance of the profile |
These measurements help you talk with the patient in objective terms and recognize limits. What the product can do is add volume. It cannot reduce the base, narrow wide alae or correct a deviated septum. For the overview, read nonsurgical rhinoplasty and, for the dorsum and tip, hyaluronic acid on the nasal dorsum and hyaluronic acid on the columella and tip.
Clinical assessment step by step
A simple routine organizes the exam before any decision.
- Profile, front and base: photograph with the same light and height. The base (seen from below) shows the symmetry of the nostrils and the columella.
- Skin: assess thickness, oiliness, scars and lesions.
- Palpation of the skeleton: locate the boundary between bone and cartilage, and feel for irregularities.
- Breathing function: ask about obstruction, deviated septum and previous surgery.
- History: rhinoplasty, previous filler, use of silicone or other materials.
- Expectation: ask the patient to show in the mirror what they want to change.
When not to treat
Some conditions usually limit or rule out treatment, at the professional's discretion:
- recent nasal surgery or incomplete healing;
- active lesions, infection or herpes in the area;
- very thin skin with little tissue reserve;
- a history of permanent filler material in the area;
- an expectation that requires reduction or functional correction;
- no setup to handle an emergency;
- a patient unable to follow the aftercare closely.
In many of these cases, referral to a surgeon is the most honest course. See the reasoning in telling a patient the procedure is outside your scope.
How to explain it to the patient
Records and consent
Document the exam, skin, history, product, lot number and instructions. The consent should name necrosis and vision loss as possible complications. The general risk picture is in vascular danger zones of the face and in safety and complications: overview.
Where Harmy comes in
Common mistakes in nasal assessment
- Assessing only from the front. Many nasal concerns only show up in profile and from below.
- Forgetting function. Obstruction, deviated septum and previous surgery change the plan and the risk.
- Promising what the product does not do. Filler adds volume; it does not reduce, slim or correct structure.
- Treating an operated nose like a virgin nose. Blood supply and tissue mobility change after surgery.
- Underestimating the skin of the tip. It is thicker but vulnerable to ischemia, and deserves its own attention.
Frequently asked questions
Why is the nose a high-risk area for injectables?
Because it has little soft tissue margin, thin skin in key areas and vascular connections with the ophthalmic system. The consequences of an occlusion can be serious, and being prepared for an emergency is essential.
What is nonsurgical rhinoplasty?
It is the use of filler to change the look of the nose without surgery. The indication, the limit and the execution are decisions for the qualified professional, and the procedure does not replace surgical rhinoplasty in every case.
What is the difference between the bony and the cartilaginous dorsum?
The upper third is bony and firm, while the middle and lower thirds are cartilaginous and more mobile. This difference changes how the area responds to volume changes and the local risk.
Can any nose receive filler?
No. Scars, previous surgery, very thin skin, a history of filler in the area and expectations that require removing tissue usually limit or contraindicate treatment, at the professional's discretion.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.