
Cosmetic Procedure Addiction: Signs and Limits
Quick facts
- Question
- Is there such a thing as cosmetic procedure addiction, and how to recognize it
- Clinical term
- Not a formal diagnosis; it may be linked to body dysmorphic disorder and other conditions
- Signs
- Constant dissatisfaction, escalating requests, rushing, disproportionate reaction to small details
- Who decides
- The professional decides whether to treat; the diagnosis belongs to a mental health professional
Every professional who has practiced for a while knows the patient who comes back every month with a new "detail" to fix. Each session brings brief satisfaction, and soon another dissatisfaction follows. This pattern has been informally called "procedure addiction." This page helps you recognize the signs, understand what is often behind them, and decide when to say no, with care and ethical backing.
Is there really an addiction?
It is not a formal diagnosis. The term is used day to day to describe the repeated and growing pursuit of interventions, with persistent dissatisfaction. Behind it there may be different conditions: anxiety, low self-esteem, perfectionism, the effect of social media and filters (filter dysmorphia), or body dysmorphic disorder, in which there is intense preoccupation with small or imagined flaws.
This distinction matters. A person with body dysmorphic disorder does not "get better" with more procedures, and the dissatisfaction tends to return or move to another part of the face. The professional is not the one who diagnoses, but is the one who can notice the pattern and act with prudence.
Which signs deserve attention?
| Sign | What it may indicate |
|---|---|
| Intense focus on a flaw you can barely see | Disproportionate preoccupation with appearance |
| Many procedures in a short time | Dissatisfaction that the result does not resolve |
| Asks for the same adjustment repeatedly | Altered perception of the result |
| Very short satisfaction after each session | Search for emotional relief |
| Compares themselves with filters or social media faces | Unrealistic expectation |
| Photos with angles and lighting that "prove" the flaw | Hypervigilance about the face |
| Intense distress, avoids mirrors, photos, or social life | Impact on quality of life |
| Strong reaction to refusal or postponement | Emotional dependence on the procedure |
| Pressure for you to do more than planned | Urgent need for change |
A single sign defines nothing. What counts is the pattern over time, and the aesthetic medical history should include the history of procedures and the person's relationship with their own face.
What to ask during the consultation
The medical history can go beyond the clinical. Open, welcoming questions help: "what bothers you most when you look in the mirror?", "how much time a day do you think about it?", "how did you feel after the last procedure?", "have you thought about doing others?". The answers say more than the initial request.
When to decline, and how
Declining is a safety tool. Patient autonomy is a value, but it does not oblige the professional to perform procedures they consider inappropriate. Declining when there is no indication, when the expectation is unrealistic, or when significant psychological distress is suspected is ethical conduct.
How to do it:
- Choose a calm moment and a private setting.
- Start with care: "I am concerned about how you are feeling about your face."
- Describe what you observe: facts, not labels.
- Explain the reason for declining: safety, lack of indication, risk of an artificial result.
- Offer a path: referral to a psychologist or psychiatrist, or another conversation after some time.
- Document everything in the patient record, including the decision and the guidance.
The procedure refusal form template can help with documentation, with legal review. See also the tone of the conversation in script for declining a procedure politely.
Risks of continuing
Repeatedly treating someone with a disproportionate request brings risks for the patient and the professional: product buildup, loss of natural look, cumulative complications, permanent frustration, and ethical exposure. A sequence of small "touch-ups" can produce a face different from the one the person had and from the one they wanted. The notion of a near miss and the documentation of events help you learn from borderline situations.
What about Harmy?
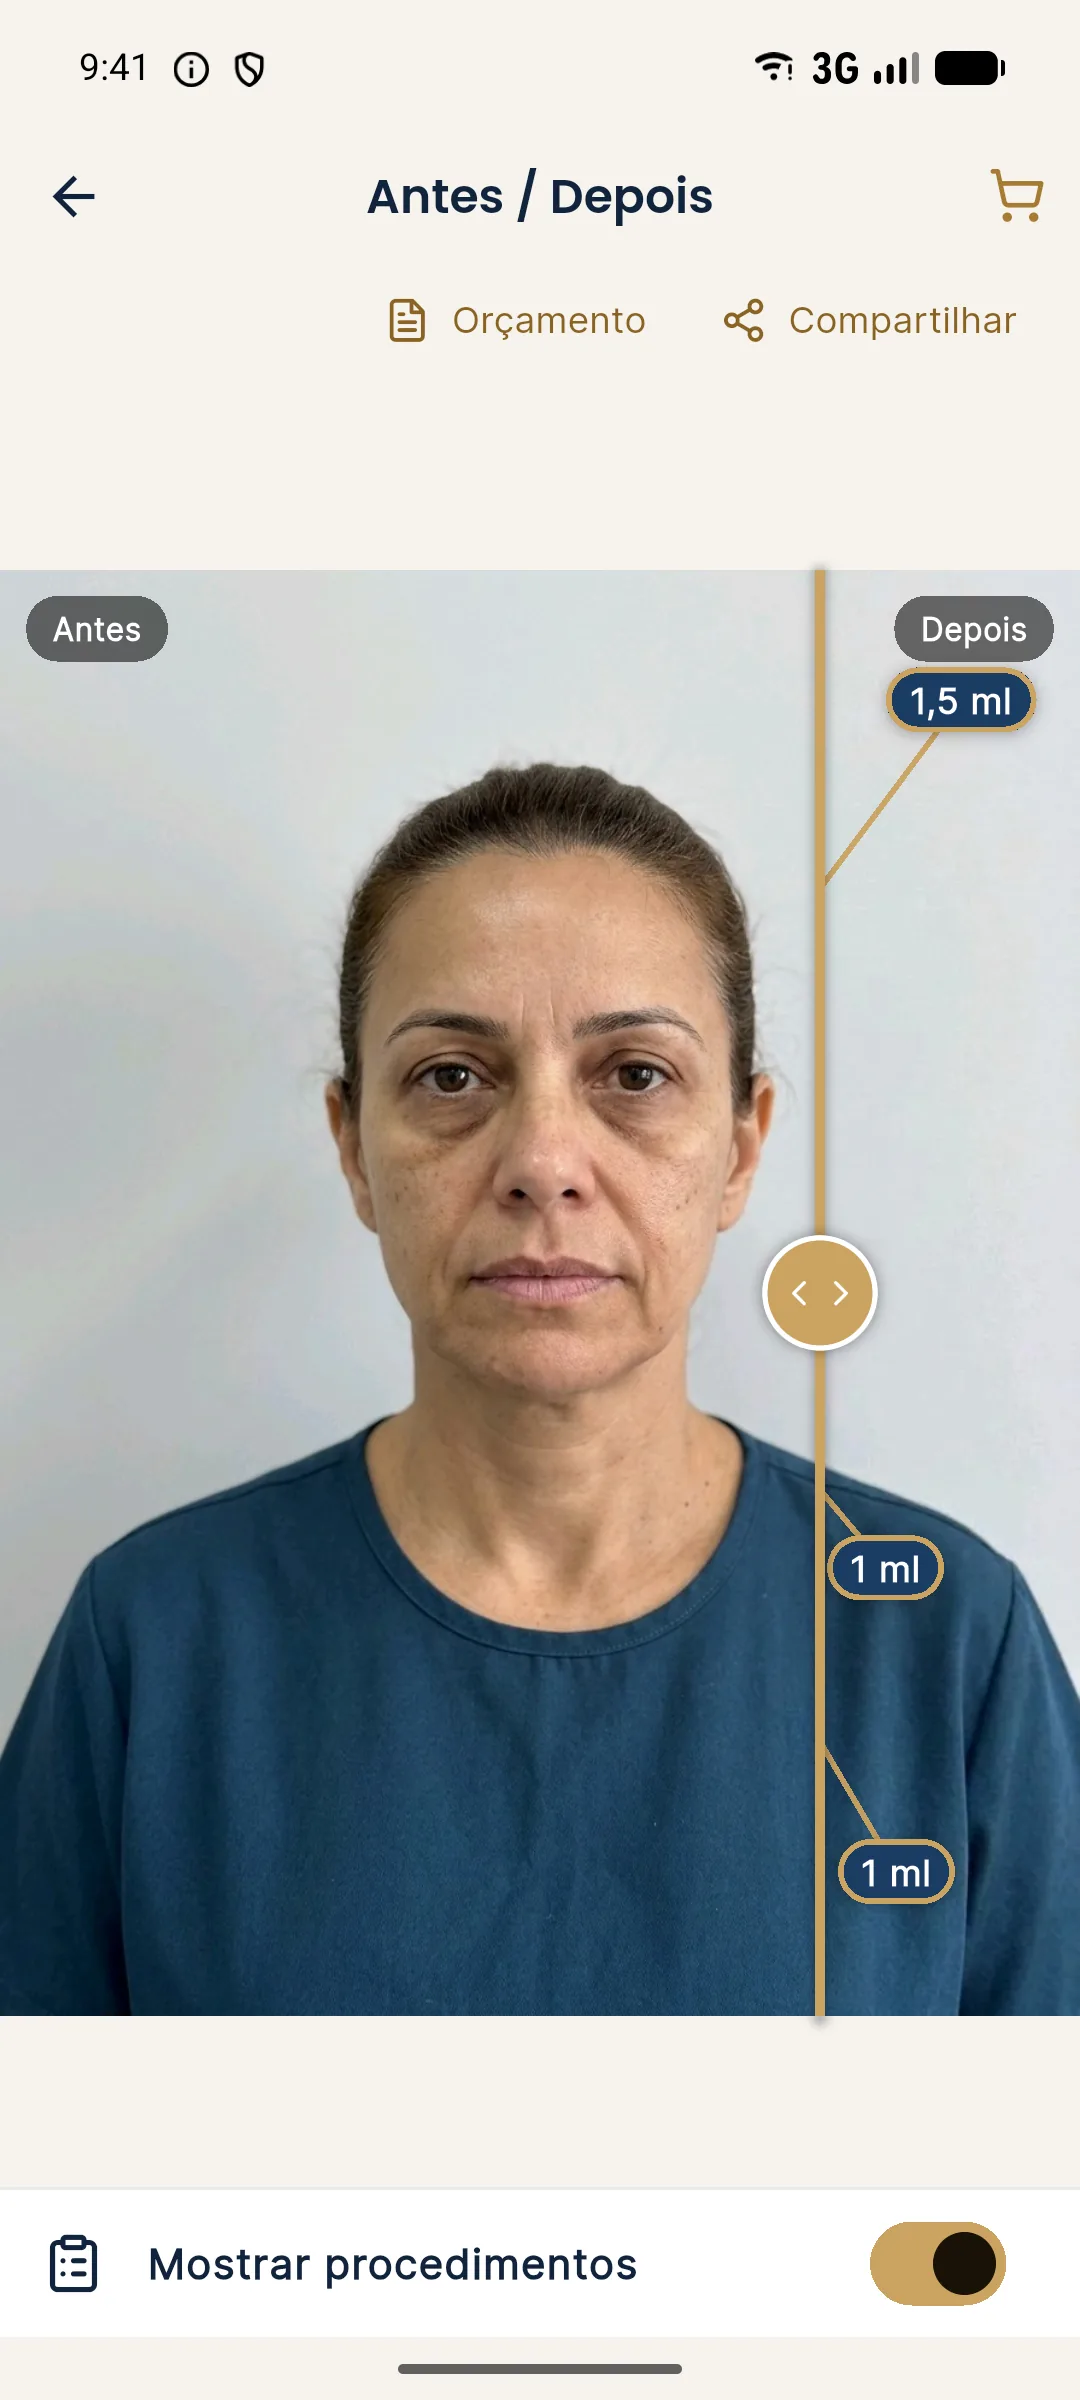
Harmy can help lead the conversation with more realism. Because the projection respects volume and does not retouch skin or change expression, it shows subtle, realistic changes. For the patient who seeks perfection, seeing that the possible result is discreet can reduce the pressure for more. The projection is an illustrative simulation, not a promise of results, and it does not replace clinical assessment or the judgment about indication.
Frequently asked questions
Is there such a thing as addiction to cosmetic procedures?
It is not a formal diagnosis, but there are patterns of repeated seeking and persistent dissatisfaction that cause concern. Many cases are linked to body dysmorphic disorder or other mental health conditions.
Which signs suggest I should decline the procedure?
A request for change that is out of proportion to the finding, dissatisfaction that does not improve with the result, a focus on a minimal flaw, a rush for new treatments, and significant distress. The professional decides case by case.
Can I refuse a patient who wants to do more?
Yes. A well-founded refusal, explained with respect and documented, is ethical conduct, and you can offer a referral.
How do I refer without offending?
Describe what you observe, show concern for the person's well-being, and suggest an assessment with a psychologist or psychiatrist as a form of care, not rejection.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.