
Deep mouth corner crease and fold beside the mouth: assessment

 BeforeSimulation
- Muscle
- Highlighted area
Quick facts
- Concern
- Deep crease or strongly marked shadow right beside the corner of the mouth
- Key reading
- Tell the commissure, marionette lines and nasolabial fold apart, since they meet in this area
- Common causes
- Muscle tightening at the modiolus, loss of support, thin skin, saliva and habits
- Main caution
- Small, mobile, highly vascular area; too much volume weighs it down and gives a droopy mouth look
The fold beside the mouth is a concern that patients describe in very different ways: "a line at the corner", "a line running down from my mouth", "a little dimple by my mouth", "tired mouth corner". For the professional, the starting point is to understand that this spot brings together four structures that blur together in a photo: the commissure itself, the marionette line, the nasolabial fold and the edge of the chin.
Here the commissure is treated as a stand-alone concern. If what bothers the patient is the sad look of the whole area, see downturned mouth corners. If the groove runs down to the chin, see deep marionette lines.
Where exactly is the commissure?
The oral commissure is the point where the upper lip meets the lower lip, at the corner of the mouth. Beside it, the skin gathers fibers from several muscles into a convergence node, the modiolus. The orbicularis oris, the buccinator, the zygomaticus major and the depressor anguli oris cross there.
That crossing explains why the area forms creases even in young faces: the skin there moves in every direction with speech, smiling and chewing. The crease, in itself, is not pathological. The concern arises when it deepens, darkens or extends downward.
What causes a deep crease?
It is rarely just one. In practice, what you see is a sum:
- Muscle dynamics: strong tightening of the modiolus, the habit of pressing the lips together, using a straw, bruxism and perioral tension deepen the crease over time.
- Loss of lateral support: volume loss beside the mouth and chin takes away support from the commissure and makes the crease deeper.
- Thin skin and loss of elasticity: repeated creases turn into static grooves. See static wrinkles and loose skin around the mouth.
- Saliva and moisture: chronic moisture buildup in the crease can darken and macerate the skin, which changes the reading and the approach.
- Teeth and dentures: missing teeth or poorly fitted dentures reduce support of the lower third (see dentures and lip support).
- Associated marionette lines: the groove running down from the corner extends the crease and adds to the sad look.
How do you tell it apart from marionette lines and the nasolabial fold?
The confusion is common, because the three grooves meet in the area. A reference table helps name each one with the patient:
| Structure | Where it is | Direction | How the patient describes it |
|---|---|---|---|
| Nasolabial fold | From the side of the nose to the mouth corner | Diagonal, descending | "Smile lines" |
| Commissure | Where the lips meet, beside the corner | Short, near the corner | "A crease at the corner" |
| Marionette lines | From the mouth corner to the side of the chin | Vertical, descending | "Puppet mouth" |
| Labiomental fold | Below the lower lip | Horizontal | "Line under the lip" |
In many cases they continue into each other, and the patient reads them as a single line, from nose to chin. Separating each stretch on the photo, with arrows, avoids treating a groove that is really a consequence of another. The nasolabial fold has its own planning rules, and smile lines call for extra vascular attention.
What fits in the plan?
The decision depends on the dominant cause. A practical line of reasoning, always subject to the licensed professional's assessment:
- Crease from lost lateral support: replacing volume in the adjacent area, in small amounts, usually has a better chance than filling the crease itself. See mouth corner filler.
- Crease from muscle dynamics: the muscular component can be discussed, with caution, because toxin near the lower lip can affect function. See toxin in the depressor anguli oris.
- Crease associated with nasolabial fold and marionette lines: plan the whole area, not the spot. See mouth corners, marionette lines and chin.
- Thin skin with static creases: improving skin quality may be the first step, before volume.
In every scenario, the area is small, mobile and vascular. Too much product in the wrong spot weighs down the corner and gives the opposite of the intended look. Possible complications include swelling, bruising, nodules, asymmetry and, more seriously, vascular occlusion. Hyaluronidase must be available and the team must know how to act. See the overview in vascular danger zones of the face.
How do you show the limit to the patient?
The classic mistake is promising to "remove the crease". In general, the realistic goal is to soften the shadow or the deepening, accepting that a movement crease will still be there. Talking about this beforehand avoids disappointment and repeated requests for "just a little more".
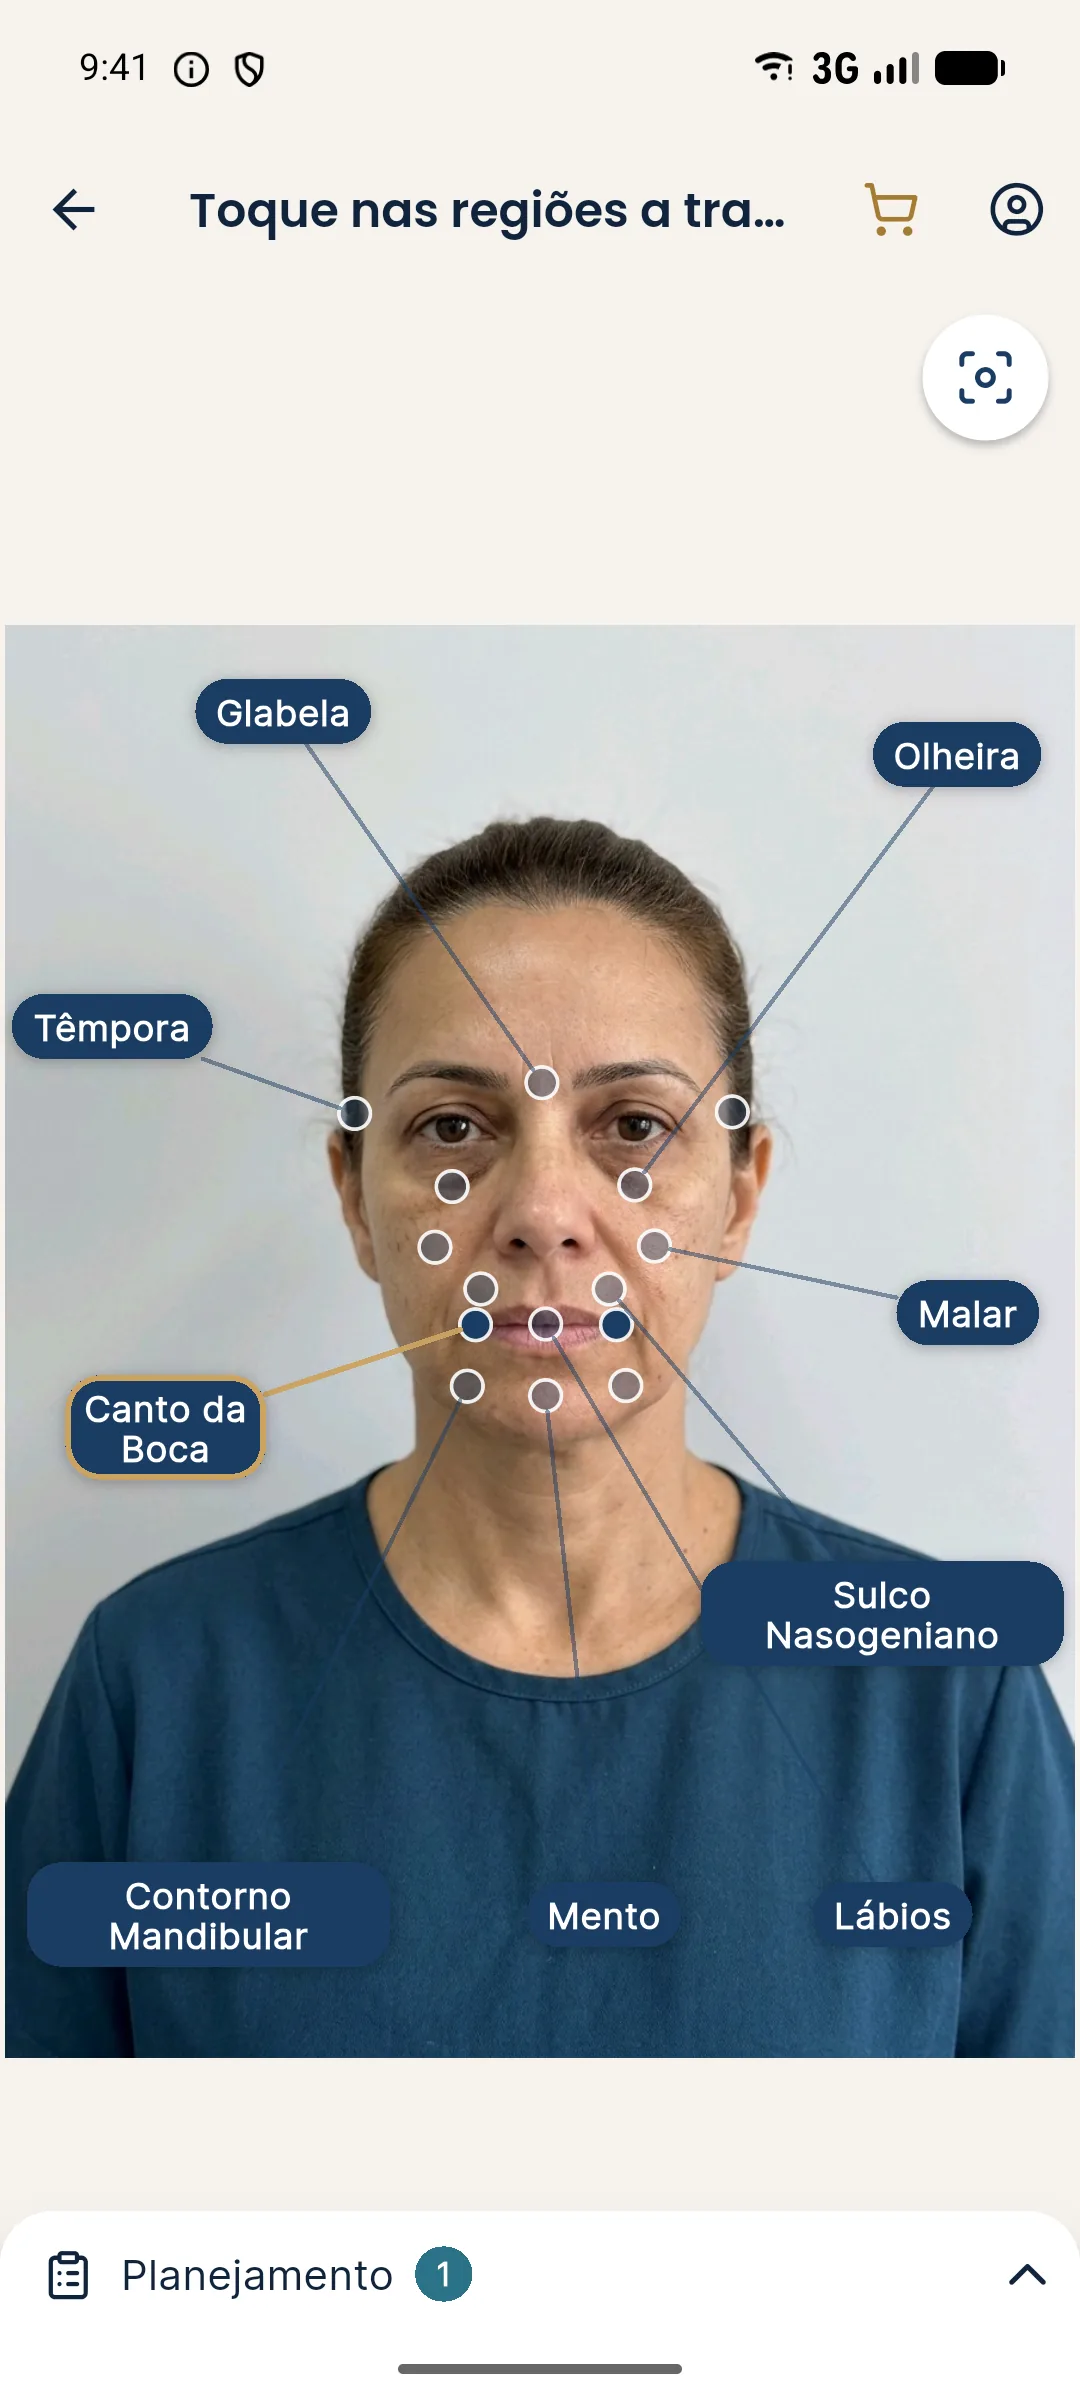
The simulation in Harmy helps show the subtle change that a small addition delivers. Since the app changes only what was marked, the visual result is restrained, which fits an area where less is usually more.
When is it better not to treat the commissure?
There are contexts where prudence says to postpone or decline. Consider not treating when:
- There is active infection, injury or inflammation at the corner of the mouth.
- The patient expects to "erase" the crease, and the expectation does not change after the explanation.
- There is suspicion of body dysmorphic disorder, with a concern out of proportion to the visible crease.
- The picture is broad laxity of the lower third, where a single spot does not solve it (see lower third laxity: assessment).
- There is a history of vascular complication in the area.
Record keeping
Photograph rest, smile and three-quarter views with the same standardization. Note the dominant cause, the approach, the agreed volume as a range and what was said about limits. The history per patient keeps sessions organized for comparison at follow-up, and the record backs up the conversation when the patient asks "but did it improve?".
Frequently asked questions
What is a deep oral commissure?
It is the crease that forms beside the corner of the mouth, where the lips meet. It can be a movement crease, a loss-of-support crease or a thin-skin crease, and it often shows up together with marionette lines.
Is a deep commissure the same as marionette lines?
No. Marionette lines are the groove running from the mouth corner down toward the chin; the commissure crease sits right at the point where the lips meet and may or may not extend downward.
Does filler fix the crease beside the mouth?
It can soften it in selected cases, at the discretion of the licensed professional, but the area calls for caution. In muscular or laxity-related creases, filler alone usually has a limited effect.
Could the crease be something else, like a sore at the corner of the mouth?
Yes. Chronic cracking and redness at the corner (angular cheilitis) have their own causes and need a clinical assessment before any aesthetic procedure.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.