
Revenue per clinical hour in facial harmonization

Quick facts
- Topic
- Revenue generated per schedule hour
- Basic formula
- Revenue for the period divided by available hours
- Caution
- Revenue is not profit, and an available hour is not a sold hour
- Use
- Comparing procedures, shifts and days of the week
The question many clinics never ask is simple: how much does each hour of the schedule earn? Monthly revenue answers how much came in. Average ticket answers how much each patient left. But only revenue per hour shows what matters to anyone who sells time: whether the available hours are being used well. Two clinics with the same revenue can have opposite realities, one with a packed schedule and a tired team, the other with half its hours empty and high prices.
This page explains how to calculate revenue per clinical hour, how to read the number, how to compare procedures by the hour and what to do when the math shows hours that do not earn. The focus is management. Clinical indication should never be driven by revenue per hour alone. For the cost of the hour, see cost of the clinical hour in facial harmonization and the clinical hour value calculator.
Two versions of the same calculation
Revenue per hour can be calculated two ways. Each answers a question.
| Version | Formula | Question it answers |
|---|---|---|
| On available hours | Revenue for the period ÷ hours the schedule was open | Is the whole schedule paying what it should? |
| On occupied hours | Revenue for the period ÷ hours actually with patients | When I am seeing patients, do my price and procedure mix earn enough? |
The difference between the two is idle time. If revenue per occupied hour is good and revenue per available hour is low, the problem is filling the schedule. If both are low, the problem may be price, mix or appointment length. If revenue per available hour is good but the team is always exhausted, the problem may be overload. See also schedule occupancy rate and schedule capacity.
Revenue is not profit, but it guides
Revenue per hour is a billing indicator. It does not deduct supplies, tax, fees or commission. A high-revenue procedure can have expensive supplies and leave little. So use revenue per hour to see the schedule and use the profit ranking by procedure to look at margin. The two readings complement each other:
- Revenue per hour tells you whether time is being sold.
- Profit per hour tells you whether the sold time is leaving money behind.
- Clinical hour value tells you how much each hour needs to earn for the clinic to make it through the month.
Compare revenue per hour with the clinical hour value. If revenue falls below the target, the schedule is not paying the cost. The break-even calculator helps estimate the target in hours.
How to measure step by step
If the clinic uses an online schedule, the number of hours comes almost ready. See online scheduling for a facial harmonization clinic and the clinic's schedule. If not, start with a simple spreadsheet, even a manual one.
Comparing procedures by the hour
To compare procedures, calculate each one's average revenue divided by its average chair time, including assessment, preparation, record keeping and instructions. The comparison often shows that duration matters more than price.
| Procedure (example) | Average revenue | Chair time | Revenue per hour |
|---|---|---|---|
| Quick procedure | (your data) | under an hour | revenue ÷ hours |
| Medium procedure | (your data) | about an hour | revenue ÷ hours |
| Long procedure | (your data) | over an hour | revenue ÷ hours |
| Assessment consultation | (your data) | consultation time | revenue ÷ hours |
| Included follow-up | zero | follow-up time | zero, but it costs time |
The included follow-up row is usually the surprise: it is schedule time with no direct revenue. That is not a reason to eliminate it, because the follow-up protects the result and the relationship with the patient, but it is a reason to know what it costs and to set a policy. See 15-day follow-up and pricing follow-up and maintenance.
What to do when the hour earns little
Before thinking about a price increase, look for the cause. Four common causes, with different actions:
- Empty schedule. Lack of demand, lack of follow-ups or too many open hours. Actions: reactivating patients, a waiting list, adjusting opening hours. See reactivating inactive patients and patient recall.
- Gaps between appointments. Poorly distributed intervals, delays and no-shows. Actions: reorganize blocks, reinforced confirmation. See no-shows at the facial harmonization clinic.
- Outdated price. Amount below the real cost. Action: price review. See annual price increase.
- Inflated appointment time. Slow preparation, disorganized records, unfocused conversations. Action: standardize the routine.
How Harmy fits into consultation time
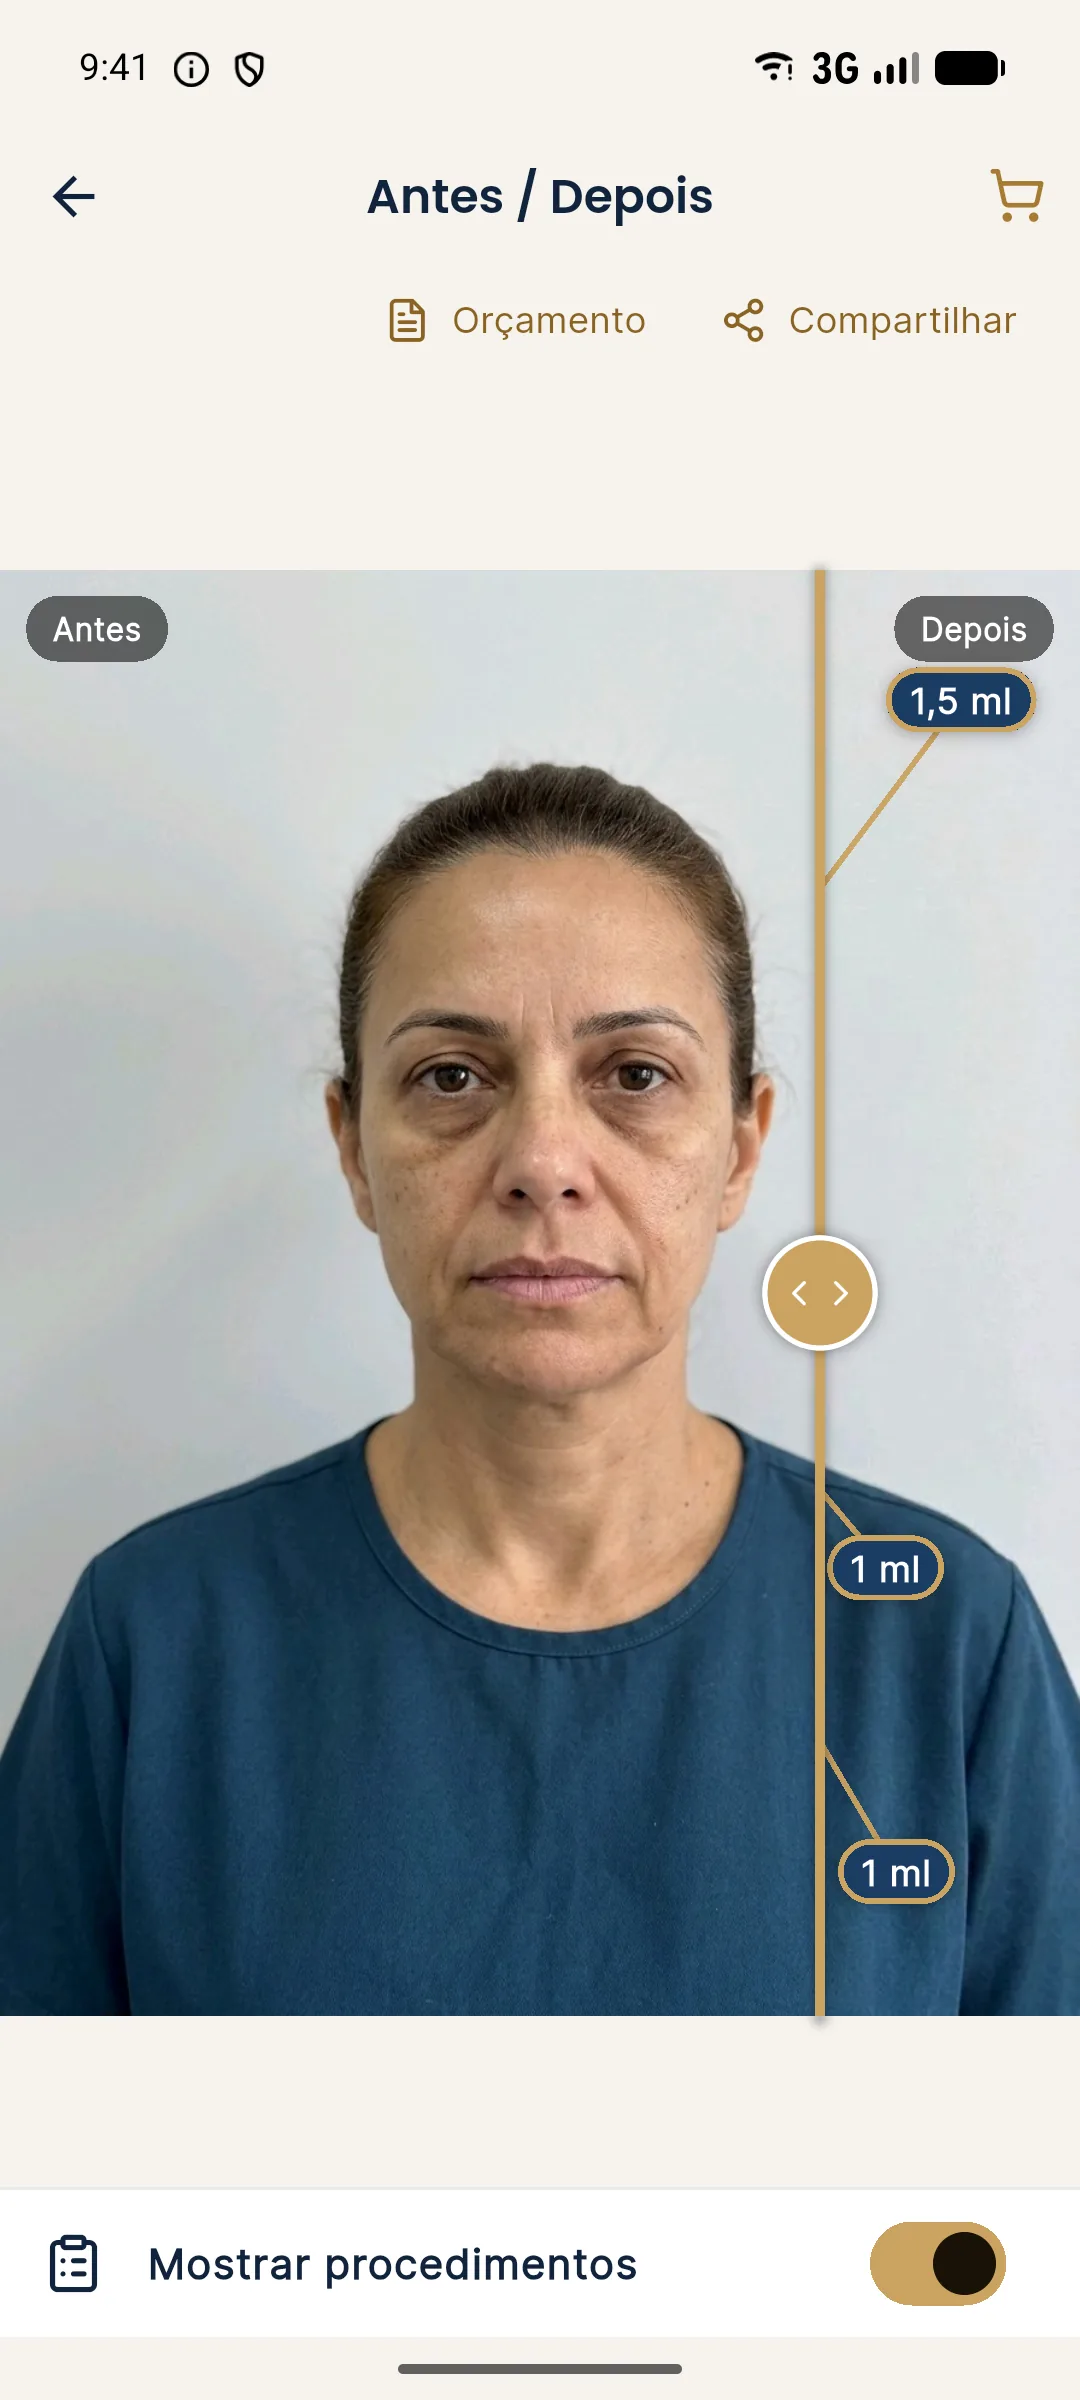
The time spent presenting the plan is part of the clinical hour. Harmy helps make that step more objective: with the frontal photo, the app detects the face, you mark the areas and the ml, generate the projection and show the before and after in a slider. Presentation mode puts the phone in full screen, with only the slider, to turn toward the patient. The conversation gets shorter and more focused, without taking away the time the assessment requires.
For the math on how much the app pays for itself, see the calculator of projections that pay for the app, and for the effect of a complete plan on the ticket, the ticket increase simulator.
Realistic targets per hour
Avoid targets copied from other clinics. Set yours in three steps: calculate the clinical hour value needed to make it through the month, estimate realistic occupancy (no clinic runs at a hundred percent without wear) and divide the revenue target by the expected occupied hours. Review it every quarter.
The best use of revenue per hour is as a monthly thermometer. It does not have to be exact or sophisticated: it has to be done the same way every time, so that the change over the months shows whether the clinic's decisions are helping or hurting.
Frequently asked questions
What is revenue per clinical hour?
It is how much the clinic bills, on average, per schedule hour. It can be calculated on available hours or on hours actually occupied, and each version answers a different question.
Are revenue per hour and clinical hour value the same thing?
No. The clinical hour value is the cost and the target for how much an hour needs to earn. Revenue per hour is what the hour actually earned. Comparing the two shows whether the schedule is paying what it should.
How can I raise revenue per hour without raising prices?
By reducing dead time between appointments, filling gaps in the schedule, organizing preparation and presenting complete plans when indicated. None of this replaces clinical assessment.
Is it worth measuring by day of the week?
Yes. Many clinics discover that certain days and shifts earn much less, and can reorganize the schedule, opening hours or the types of procedure in each shift.