
Filter face: how to handle unrealistic references

Quick facts
- Topic
- Unrealistic references brought by the patient
- Source of the problem
- Filters, image editing and flattering angles
- Professional's stance
- Welcome the desire and translate it into real possibilities
- Limit
- Facial harmonization does not change bone or reproduce a filter
- Caution
- Signs of disproportionate dissatisfaction call for attention
The patient walks into the office with a phone in hand and an image on the screen. It might be a filtered selfie, an edited photo, a photo of a celebrity or a face generated by artificial intelligence. The line is usually the same: "I wanted to look like this." That reference is the hardest starting point of the consultation, because it mixes a legitimate desire with an image that never existed outside the screen. This page covers how to handle it without frustrating the patient or promising the impossible.
What does a filter do that facial harmonization does not?
A filter modifies the image continuously and without anatomical limits. It can smooth skin, change the proportion between eyes and mouth, slim the nose, project the chin and redraw the contour without regard for bone, muscle, fat or ligament. Facial harmonization, by contrast, works within real anatomy: it injects small volumes into specific areas, and the result depends on each person's tissue.
The most important differences are these:
| Aspect | Filter | Facial harmonization |
|---|---|---|
| Anatomical limit | None | Always present |
| Skin texture | Artificially smoothed | Preserved |
| Symmetry | Can be perfect | Natural asymmetries remain |
| Movement | The image is still or smooth | The face moves and changes expression |
| Reversibility | Total and instant | Partial and dependent on the material |
| Bone and profile | Redrawn | Not changed by filler |
Showing this table to the patient, in plain language, often opens the conversation. The idea is not to dismiss the desire but to anchor it in what is possible.
Why does the desire for a filter face arise?
Many people spend hours seeing themselves on screens with automatic adjustments. The "edited" face becomes familiar, and the real face feels strange. This phenomenon is described in the literature as self-image distortion and deserves to be heard. The patient is not being shallow: they are comparing themselves with a version that exists only in the camera. See mirror, selfie and photo: differences in self-image and is there an ideal facial aesthetic?.
How do you lead the conversation?
The sequence below avoids direct confrontation and leads the patient to look at their own face with new questions.
In the "separate" step, placing the patient's real photo next to the reference is useful, as long as the tone is one of curiosity and not cruel comparison. The goal is for the patient to notice the structural differences themselves.
What do you say when the request is impossible?
Be direct and careful. Say what is not possible plainly and follow right away with what is. Avoid mocking the reference or the filter. If the request involves a bone change, such as shortening the width of the face or changing the angle of the jaw, say that facial harmonization does not do that and, where relevant, that other specialties assess these issues. Do not promise an "almost identical" approximation. See when bone is the problem, not volume and how to say no to the patient in facial harmonization.
How do you use the simulation without feeding the fantasy?
This is a delicate point. A strongly marked simulation can fuel the expectation that the result will match the filter. A subtle, honest simulation shows what is possible. In Harmy, the projection is made from 1 frontal photo, keeps skin, expression, hair and background, and changes only the marked areas, with the intensity Subtle, Moderate or Pronounced. This is useful precisely because the resulting image looks like the same face, with discreet adjustments.
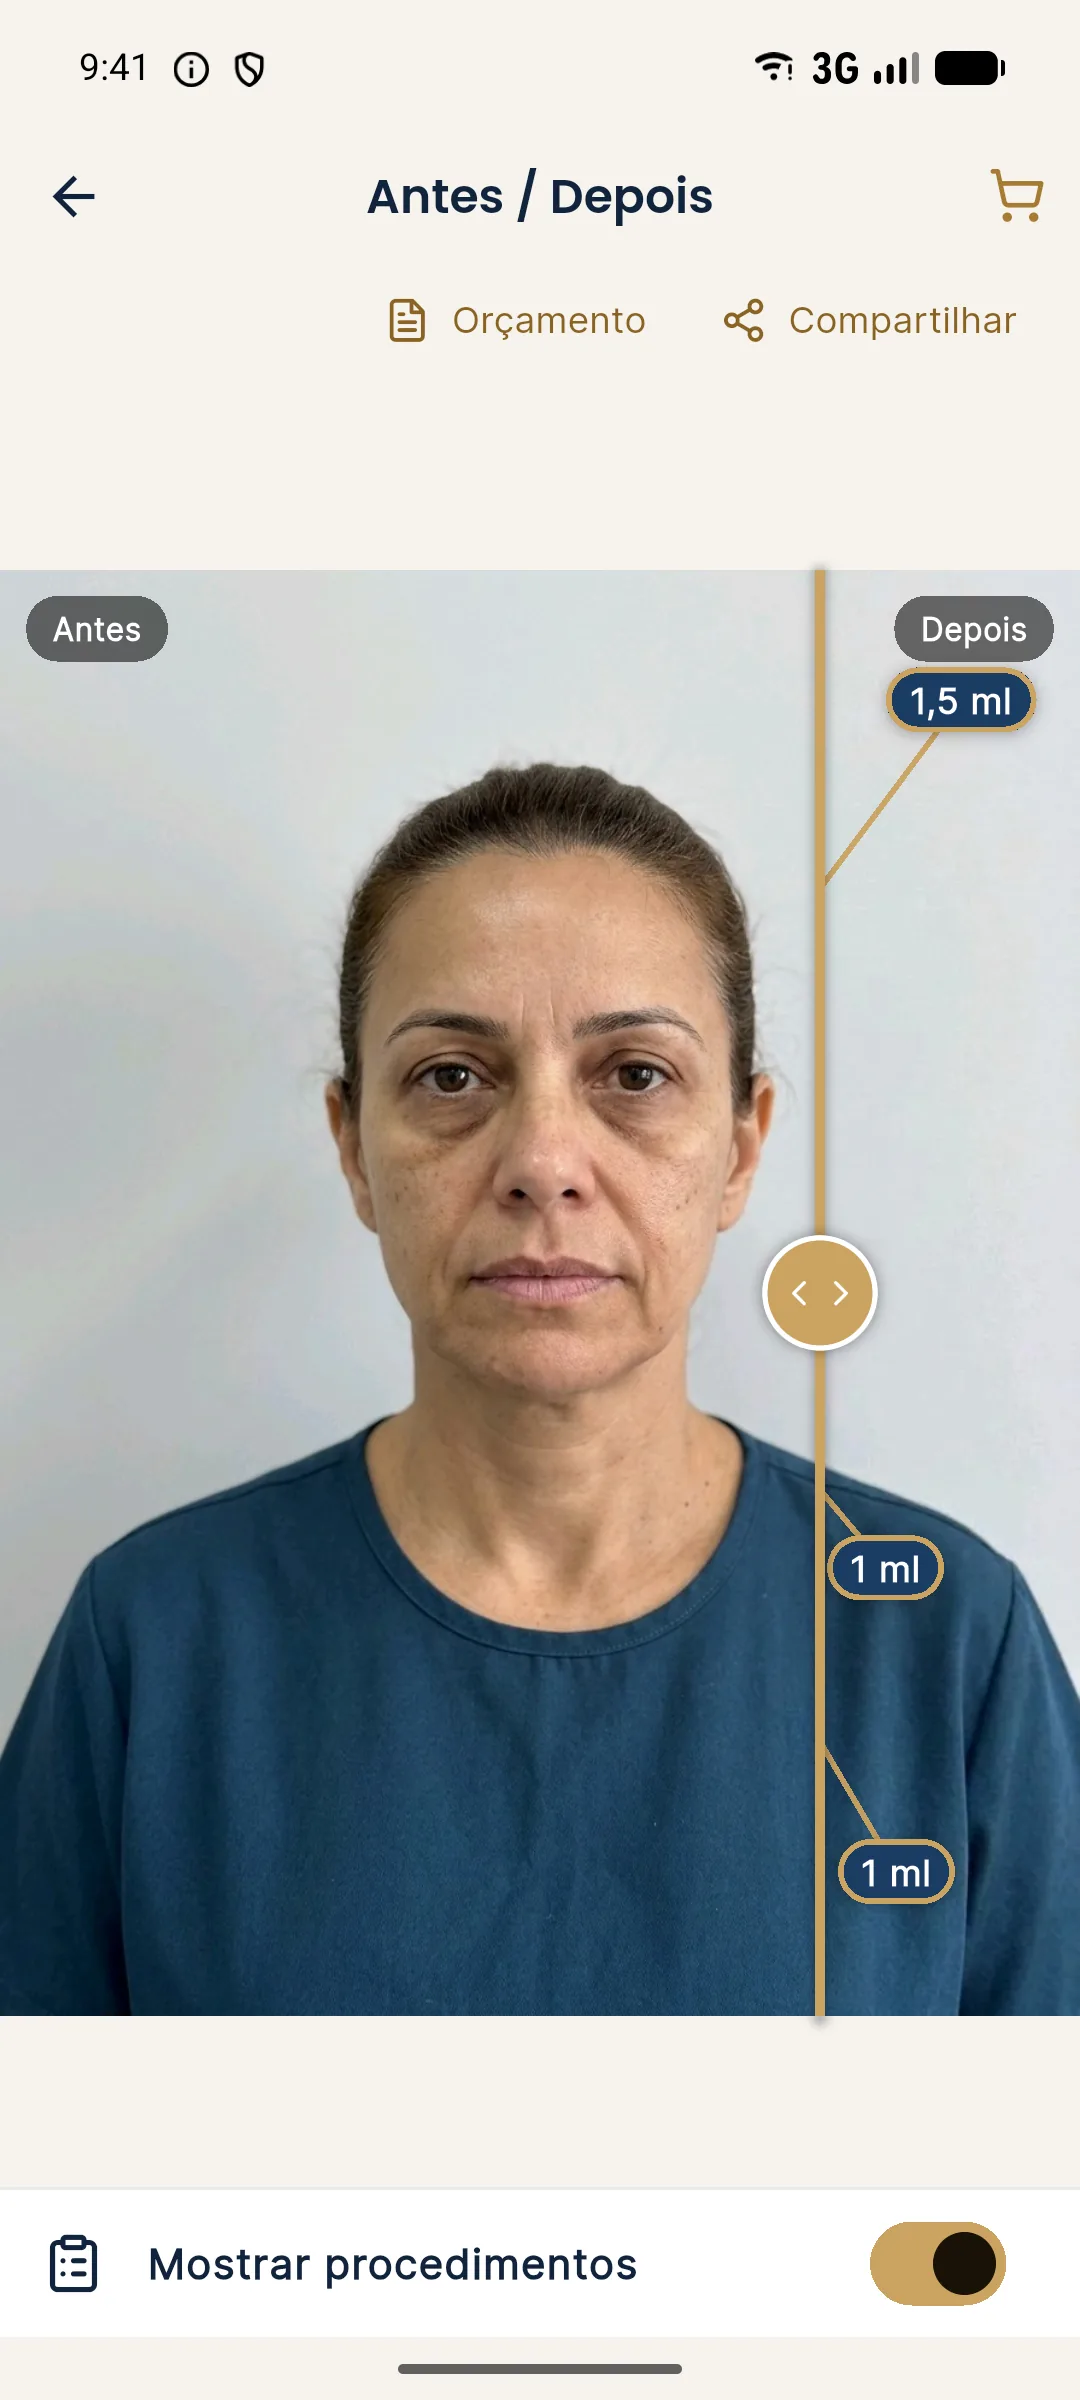
To go deeper on the honest use of the image, see why the simulation should be subtle, ethics of result simulation and simulation to calibrate expectations, not to sell.
When should you decline the plan?
There are situations in which the plan should not move forward: persistently unrealistic expectations, a request that distorts the face, pressure for an impossible result or demands for a guarantee. Declining respectfully, offering alternatives and leaving the door open for a future conversation is a form of care. Record the reasons and the alternatives offered. See saying no to a request for a guarantee and when to say no to an aesthetic plan.
And what about pressure from social media?
Patients also arrive influenced by other professionals' profiles that show extreme results, sometimes edited. Do not compare yourself with or criticize colleagues. Focus on what you can do, how you work and why you prefer discreet results. Reinforce the idea that a good result is one people perceive as "they look well," not "they had something done." For communication stance, read expressionless face: how the plan avoids the effect and natural-effect plan.
What record should you leave from this consultation?
Note the reference the patient brought (without archiving a third party's image if there is no need), what the patient said attracts them to it, what was explained as possible and as impossible, and the agreed plan. If the patient agreed to a conservative first phase, record the reassessment date. If the plan is declined, write the reasons objectively and respectfully, without judgments about the person. This record is useful if the patient seeks another professional and later returns, and it protects the clarity of what was said.
What if the patient has already had other procedures to reach the filter?
Ask calmly about the history: how many times, in which areas, with whom and why. Patients chasing an unrealistic reference often accumulate injections without satisfaction, and the face may already show excess. Before any new injection, reassess what is there, as in plan to correct previous excess. Often the best course is to pause, observe and, when indicated, reduce.
Frequently asked questions
What should I do when the patient brings a filtered photo as a reference?
Welcome it and find out what attracts them in the image. Then explain, using the patient's real photo, which features are achievable, which depend on structure and which exist only in the filter.
Can the simulation reproduce the filter face?
That is not the goal. Harmy's projection changes only the marked areas, subtly and realistically, and should not be used to reproduce a filter. It illustrates a possible plan.
How can I tell whether dissatisfaction with the face is disproportionate?
Signs include an obsessive focus on details almost no one notices, repeated requests without satisfaction and intense distress about appearance. In these cases, the professional should consider an appropriate referral.
Can I decline the plan if the expectation is unrealistic?
You can and, sometimes, should. Document the conversation, explain the limits and propose alternatives. The decision is the professional's, based on their assessment and their professional council's rules.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.