
Plan to Correct Previous Filler Excess
Quick facts
- Topic
- Correcting filler excess done before
- First step
- Identify the product, the area and the time since the treatment
- Most cited tool
- Hyaluronidase, when the material is hyaluronic acid
- Caution
- Dissolve in stages and reassess before adding new volume
- Ethical risk
- Blaming the colleague or promising to "go back to natural"
Receiving a patient with filler excess placed by someone else, or by you years ago, is a delicate situation. There is emotion, distrust and, often, an expectation of "going back to natural" that the tissue does not always deliver. This page organizes the reasoning of the correction plan: what to investigate, when to consider hyaluronidase, how to wait, how to rebuild and how to speak without criticizing the colleague.
How do you confirm that there is excess?
What the patient calls excess may be too much volume, volume in the wrong place, migrated product, an inflammatory reaction, late swelling or simply a perception distorted by self-image. Examine at rest, when smiling and in motion, with side lighting, and compare with old photos, if they exist. Telling the causes apart changes the approach. See excess volume after filler, overdone face from fillers and heavy face from old filler.
If warning signs appear, such as severe pain, skin color change or visual disturbance, treat it as an emergency. See safety and complications: overview.
When should you wait before acting?
Residual swelling, inflammatory reaction and natural reabsorption can reduce the look of excess over time, and rushing can lead to dissolving more than necessary. If the treatment was recent and the patient has no warning signs, consider an observation window with photos. Waiting is also an approach, and the patient needs to understand why. With a heavily displaced volume or local signs, waiting does not hold up, and the decision is the professional's. See late swelling after hyaluronic acid and swelling gets in the way of comparing results.
When does hyaluronidase come into the plan?
When the material is hyaluronic acid and there is a clinical indication: obvious excess, migration, a nodule, Tyndall effect or an informed request from the patient. It does not act on other materials, such as toxin, hydroxyapatite biostimulator or PMMA, so identifying the product is essential. When the product is unknown, the approach is more cautious, and prudence calls for explaining to the patient that the result is less predictable. Details in hyaluronidase in the clinic, hyaluronidase: allergy and testing and explaining hyaluronidase to the patient.
| Situation | Usual reasoning to consider |
|---|---|
| Mild excess, known product, no signs | Observe and reassess before dissolving |
| Obvious excess, hyaluronic acid confirmed | Dissolve in stages, reassessing at each step |
| Nodule or bluish color | Assess the type of reaction and the specific approach |
| Unknown product | Caution, a frank conversation and, if possible, investigation |
| Vascular signs | Treat as an emergency |
Two frequent patient questions: does hyaluronidase remove all the filler? and does hyaluronidase hurt?. The specific risks (local reaction, swelling, hypersensitivity) are part of the informed consent. Doses and dilution are the professional's decision and are not on a public page.
How do you dissolve without creating a new problem?
The central idea is to do less than seems necessary and reassess. Dissolving in stages lets you see the result and stop if the face's thin support begins to show. The patient must be told that swelling will occur and that the immediate look is not the final one. Record photos before and after, in the same framing. Re-treatment, when indicated, only happens after the tissue has settled. Read refilling after hyaluronidase and re-planning after hyaluronidase.
How do you speak without criticizing the colleague?
There is nothing to gain from pointing fingers. The patient is usually fragile, and any criticism of the colleague can sound like marketing. Describe what you see ("there is more volume than the support of the face accommodates") and what you propose ("we will reduce it in stages"). Avoid adjectives about the technique and never name names. Record clinical facts in the patient record, objectively. See also aligning expectations when changing professionals and comparing plans from two professionals.
How do you plan the new volume?
After the correction, the plan starts over with the golden rule: less than it seems. Ask why the excess happened: the patient's request, technique, lack of reassessment, accumulation of procedures or an unsuitable product. Fix the cause in the new plan. Often, the new plan is shorter than the previous one. See minimum viable plan in facial harmonization, conservative volume in the first session and when total volume becomes excess.
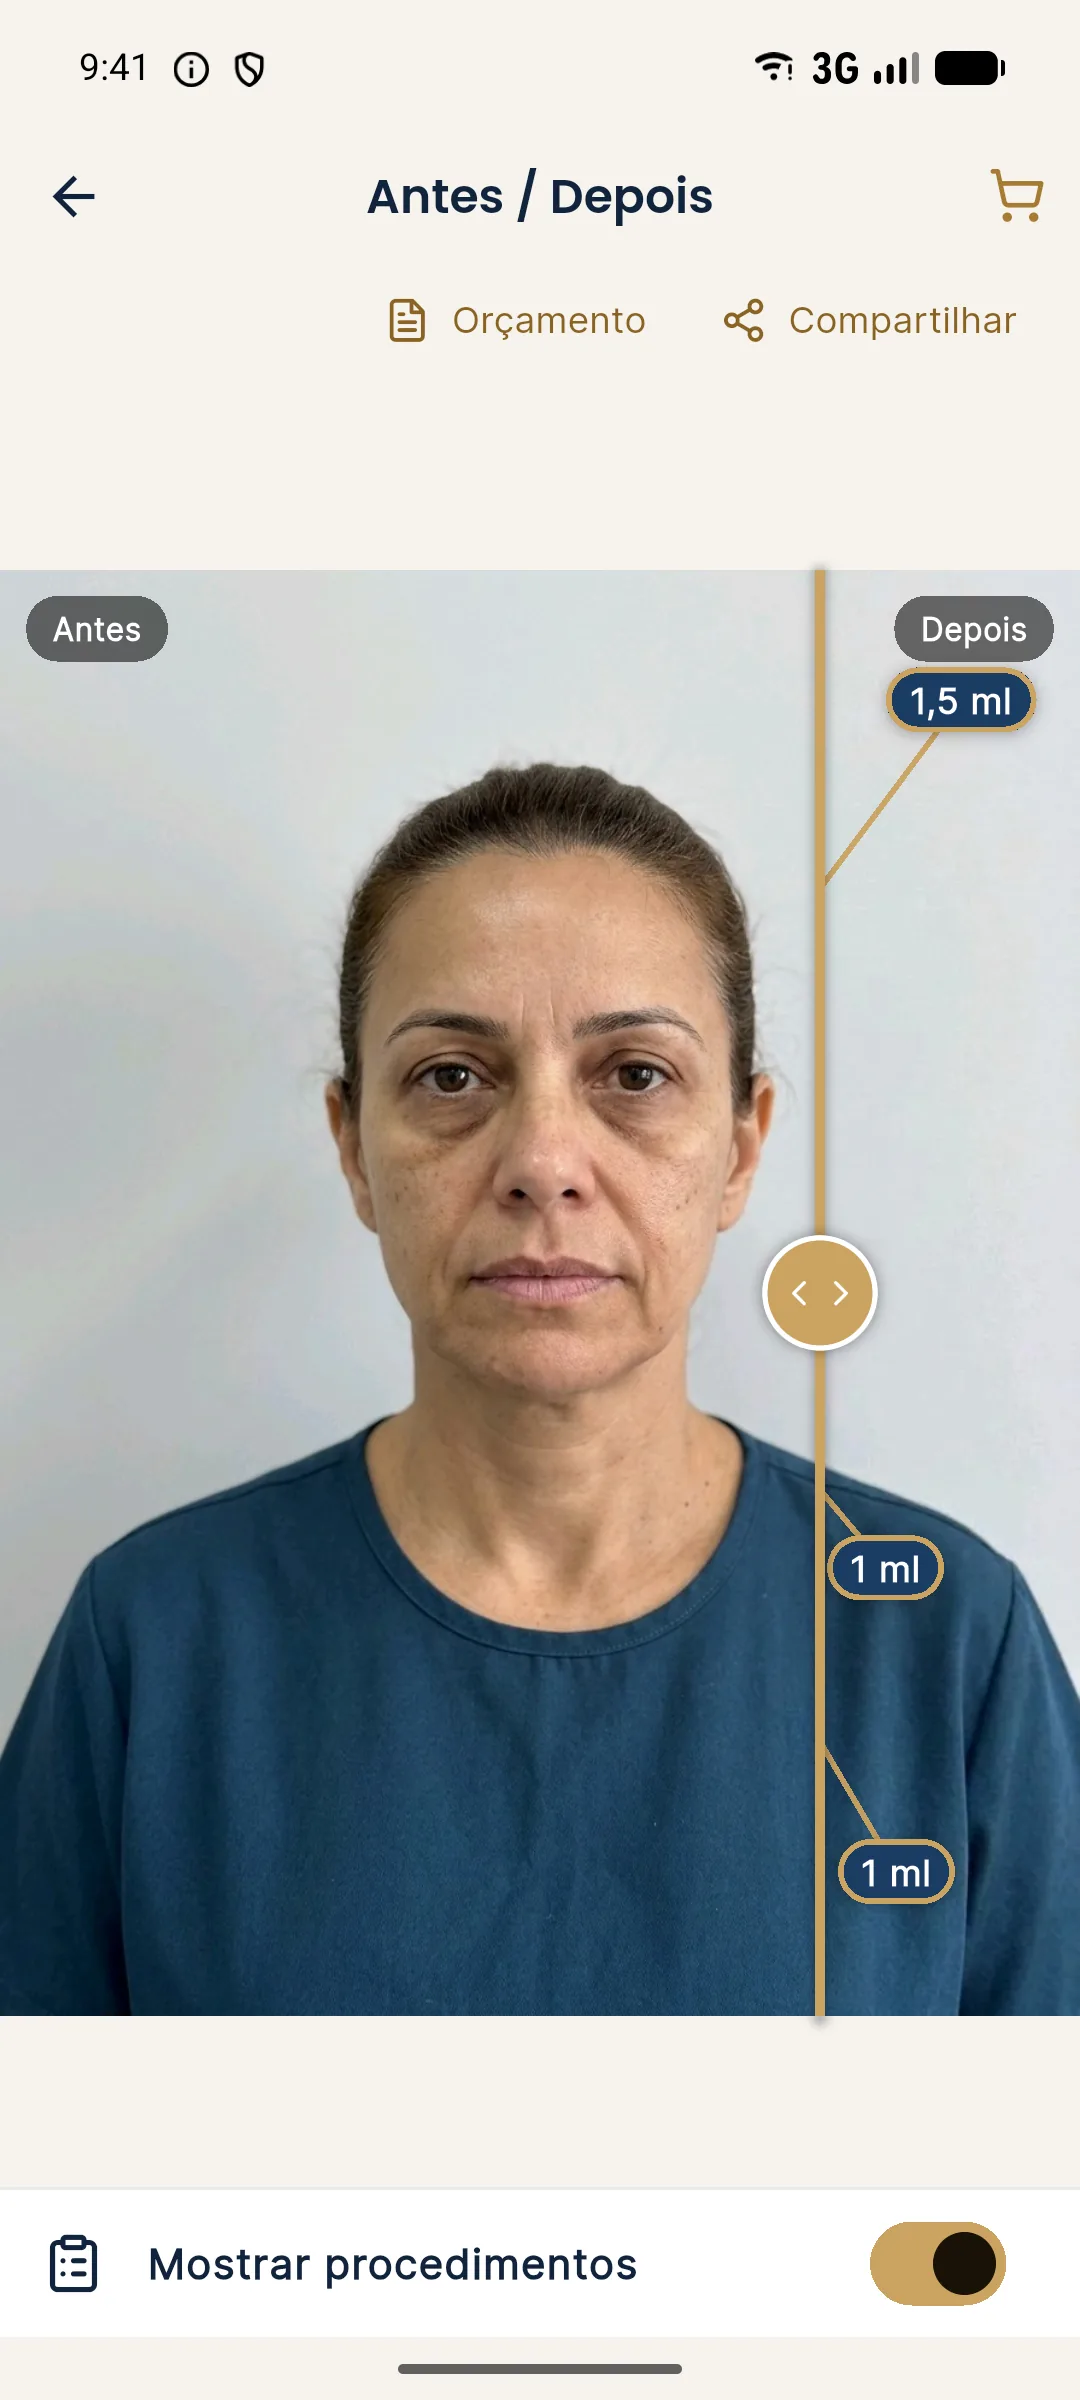
In Harmy, the projection can help design the new plan with less volume. But it only adds volume to the photo, and it does not show the face after dissolving the previous material. If the patient's photo already shows excess, the projection starts from it, which limits its use. In that case, use the history and old photos as the clinical reference, and the projection only as support.
What should you record?
Everything, objectively. Record the product (if known), the location, the estimated date of the previous treatment, the concern, the photos, the approach, the consent for dissolving and the signs observed. If the product is unknown, record that too. In case of an adverse event, follow the notification flow in adverse event reporting: Notivisa (Anvisa's system, in Brazil). See also traceability of injectables.
Reasoning quiz
Summary
Correcting excess starts with confirming the problem, identifying the product and deciding whether dissolving is necessary. Dissolve in stages, wait for the tissue to settle, record everything and rebuild the plan with less volume. The language is one of facts, without blame and without promises.
Frequently asked questions
Does every filler excess need to be dissolved?
No. Many cases are swelling, well-placed product in moderate excess, or a matter of expectation. The assessment defines whether there is an indication to dissolve, wait or simply adjust the plan.
Can I dissolve filler placed by another professional?
You can, if the product is hyaluronic acid and there is an indication, after assessment and consent. Whenever possible, try to identify the product, and avoid comments that discredit the colleague.
How long should you wait before rebuilding volume?
In general, you wait for the swelling and the reaction to hyaluronidase to resolve, and reassess calmly. The exact interval is set by the professional according to the case.
Does the simulation help correct excess?
It helps design the new plan with less volume, but it only adds filler volume (toxin only in the glabella and the chin). It does not show the face after the material is dissolved.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.