
Replanning the face after a complication in harmonization

Quick facts
- Topic
- Resuming the plan after a complication
- Priority
- Clinical management and follow-up, then the plan
- Before resuming
- Resolution of the complication and tissue assessment
- Communication
- Transparent, documented and without pressure to continue
- Resumption
- Short steps, conservative volume and new informed consent
No injectable procedure is free of complications. Significant swelling, bruising, a nodule, a marked asymmetry and, in the most serious cases, vascular compromise are all part of the risks the patient needs to know about before accepting the plan. When one of them happens, the facial harmonization plan changes nature: it stops being an aesthetic project and becomes a recovery schedule. Only after that does it make sense to talk about resuming.
What comes before replanning?
The order matters. First, clinical management: recognize, treat and follow up on the complication according to your protocol and your professional council's rules. Second, communication with the patient: explain clearly what happened, what was done and what will be monitored. Third, complete documentation. Only after these three steps does the plan return to the table.
Applying the plan before that is a mistake with a double cost: clinical, because the tissue is not yet stable, and relational, because the patient feels the priority was to keep selling. See contingency plan in facial harmonization and communicating a complication to the patient.
How do you assess whether the plan can resume?
A list of conditions helps avoid decisions made in a rush or under patient pressure.
If any item is pending, the resumption can wait. Patients generally appreciate the caution.
What changes does the plan usually undergo?
| Aspect of the plan | How it usually changes | Reason |
|---|---|---|
| Pace | More spaced-out steps | Give the tissue and the patient's confidence time |
| Volume | Lower at the start | Observe the response before increasing |
| Area of the complication | Avoided for a while or approached differently | Safety and patient preference |
| Number of areas per session | Fewer | Reduce cumulative risk |
| Documentation | More detailed | Traceability of decisions |
| Reassessment | More frequent | Catch problems early |
See when to split the volume across sessions and how many areas to treat per day. The logic is the same as for any prudent plan, only stricter.
How do you talk with the patient about continuing?
Avoid any feeling of pressure, which is the worst mistake at this point. Make it clear that they can decide to stop, wait or change professionals, and that your commitment is to safety. Ask how they feel, what worries them and what they want to do. Many patients continue precisely because they felt well cared for during the complication, and others give up. Both paths are legitimate.
For the ethical basis of this conversation, read when to say no to an aesthetic plan and informed consent.
What should the consent record?
The original consent covered the known risks. After a complication, many practices update it to record that the patient was informed of what happened, the options and the risks of resuming. The exact wording should be guided by legal counsel and your professional council's rules. What matters most is that the patient has time to read, ask questions and decide without hurry. For the document itself, see informed consent form by procedure.
And the simulation, when does it come in?
Only once recovery is well under way. Showing a projection to a patient who is still recovering can be read as insistence. When it does come in, use the image to discuss more conservative alternatives, such as lower volume, another area or a longer interval, and not as an incentive to resume. In Harmy, you create the projection from the current photo, mark a few areas and set the ml and intensity (Subtle, Moderate or Pronounced). The AI changes only what was marked and produces subtle differences.
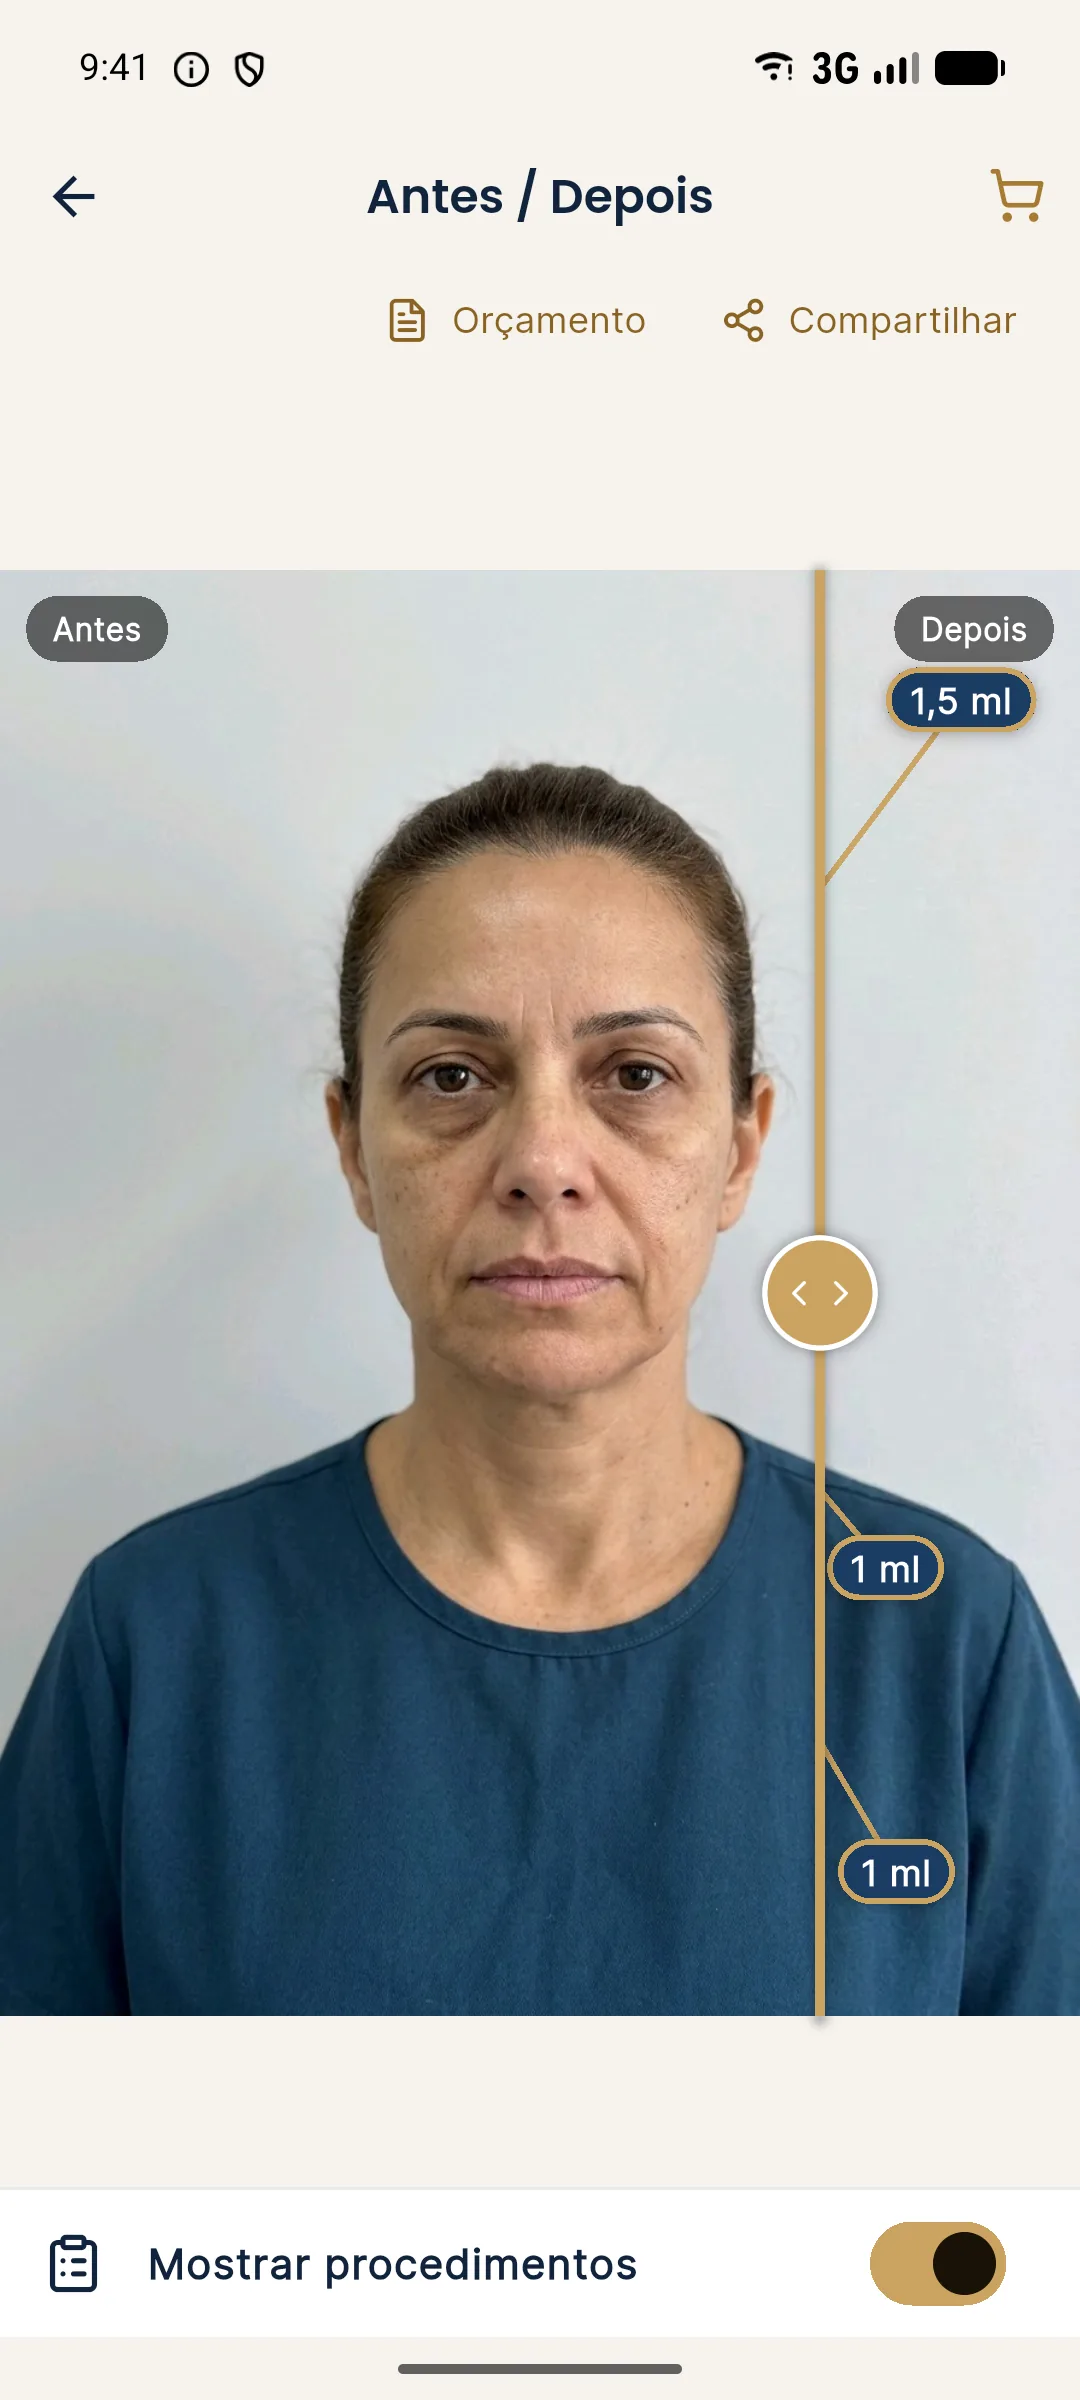
See when the simulation gets in the way of the plan and limits of 2D simulation.
What should you record for the future?
Keep complete documentation of the complication: date, signs, management, progress, communication with the patient, photos and follow-up. When resuming, record the new plan, the new consent and the precautions taken. If the patient changes professionals, the information goes with the patient and, with their authorization, between colleagues, as in handing over a plan between professionals. This history also protects the patient in future care, at any clinic.
Scheduled reassessments after resuming are part of the plan. See reassessment at 3, 6 and 12 months and replanning after hyaluronidase, useful when management included dissolution.
How do you keep the complication from happening again in the new plan?
After the event, it is worth rebuilding the reasoning with direct questions. Was the area high-risk? Was the volume within what the tissue tolerates? Was there a patient factor, such as anticoagulant use or a previous scar, that did not weigh enough? Did schedule pressure influence the decision? Answering honestly is not empty self-criticism, it is the basis of a safer plan. See prioritizing by risk in the plan and medical history in facial harmonization.
Also review the practice's setup for emergencies: dissolution supplies, the written protocol, the reference contact for referrals and team training. A safe plan depends as much on the clinical decision as on how well the setting is prepared. This review does not have to be bureaucratic; a short list, checked on a fixed date, already changes the picture.
What if the patient decides to stop?
Respect it. Hand over a summary of what was done, the follow-up instructions and an open door to return later, without pushing. The patient who leaves feeling well looked after, even if they give up, is the one most likely to come back when ready, and the one who speaks best of the care. Record their decision and the date. See exit plan from harmonization.
Frequently asked questions
When can I resume the plan after a complication?
When the complication is resolved or stable, the tissue has been assessed and the patient is comfortable moving forward. The timing is clinical and individual, set by the professional, who may also consult another specialist when needed.
Does the patient need to sign a new consent form?
Many practices update the consent and document the conversation about what happened before resuming. Confirm what your professional council's rules and your practice's legal advice call for.
Should the area of the complication be treated again?
It depends. Some professionals avoid the area for a longer period or change approach. The decision takes into account the type of complication, the recovery and the patient's wishes.
Can I use the simulation to restart the conversation?
Only once recovery is well under way, and with care. The image is illustrative and should not feel like pressure to continue or a promise that everything will be fine.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.