
Thin lips: how to assess before recommending filler

A thin lip is a lip with little vermilion showing relative to the face, whether from birth or from aging. In the office, it is one of the most direct complaints ("my lips are too thin") and, at the same time, one of those that hide the most different causes. Before recommending lip filler, it is worth finding out why that lip looks thin, because the answer changes the plan.
This guide covers assessment, at a review level. Volumes, technique, plan and instrument are decisions for the licensed professional, according to the rules of their professional council. The general anatomy of the area is on the page for the lips area.
Why assess before filling?
Filling a thin lip without assessing the cause is the shortest path to two results the patient does not want: the lip that looks "puffy", projected too far forward, and product that migrates past the border. Both appear when you try to solve with volume a problem that is not about volume.
A thin lip also tends to have little tissue to receive product. Thin mucosa and muscle accept less volume per session, and the line between "fuller" and "artificial" is narrow. A good assessment defines how much the tissue can take, what else needs to be treated and what filler will not change.
What are the causes of thin lips?
The table summarizes the most common causes, how to recognize them and what tends to help. Many patients have more than one.
| Cause | How to recognize it | What tends to help | What filler does not fix |
|---|---|---|---|
| Constitutional (little vermilion) | Thin lip since youth, healthy tissue, good height | Conservative filler, in stages | Changing the person's lip type |
| Aging | Volume loss, less defined border, lip lines | Gentle replacement, discreet contour, care with perioral skin | Lengthening of the upper lip |
| Long upper lip | A lot of skin between nose and mouth, little tooth exposure at rest | Proportion assessment; other approaches depending on the case | Shortening the lip |
| Lack of dental support | Retroclined teeth, tooth loss, ill-fitting denture, loss of vertical dimension | Dental assessment of support | Replacing the support from the teeth |
| Inversion when smiling | Vermilion disappears when the patient smiles | Assess botulinum toxin, at the professional's discretion | The muscle dynamics |
| Perception or external reference | Proportionate lip, request based on another person's photo | Conversation about proportion and simulation | Unrealistic expectation |
How to assess lip proportion?
Look at the lip within the face, not in isolation. Some practical parameters:
- Relationship between upper and lower lip. In many faces the lower is fuller than the upper. Aesthetic references often cite ratios close to 1 to 1.6, but they vary between ethnicities and between people. Inverting the relationship tends to look artificial.
- Mouth width. Wide, thin lips call for a different strategy from short, thin lips: volume concentrated in the center can create a "beak".
- Border design. Assess Cupid's bow, the columns of the philtrum and the sharpness of the border. Sometimes the lip looks thin because the contour has faded, not because it lacks body.
- Tubercle and central projection. The presence or absence of central volume in the upper lip changes the reading of "full" or "thin".
- Asymmetries. Record them before, at rest and smiling, so as not to attribute to the procedure a difference that already existed.
Facial assessment by thirds helps place the lip height within the lower third.
Why does upper lip height matter?
With age, the upper lip tends to lengthen and show less tooth at rest. The patient perceives this as a "thin mouth" or a "drooping mouth", but the cause is length, not volume.
During the assessment, observe:
- Exposure of the upper incisors at rest, with the patient relaxed and lips slightly parted. In young adults a small band of tooth usually shows, which decreases with age.
- Distance between the base of the nose and the lip border, relative to the rest of the lower third.
- Vermilion inversion: long lips tend to "roll inward".
Filling the vermilion of a long lip may even restore some exposure, but it tends to accentuate forward projection without correcting the length. Explaining this to the patient avoids the pursuit of "just a little more" at every session.
How does dental support change the assessment?
The lips rest on the teeth and the alveolar bone. Retroclined teeth, tooth loss, ill-fitting dentures and loss of vertical dimension leave the lip without support, and it thins and "sinks" inward.
This is a point where a dental perspective makes a difference. If the support is compromised, filler tries to compensate with volume for what is missing in structure, and the result is usually worse. In these cases, assessing or referring the dental issue may come before, or alongside, the lip plan.
How does the profile factor into the assessment?
Seen in profile, the position of the lips depends on the nose and chin. The nasolabial angle and references such as the Ricketts line help show whether the lips are projected, retracted or balanced in the facial profile.
A retracted chin can make the lower lip look everted and the upper one disproportionate. Sometimes what the patient reads as "lack of lip" is lack of chin, and the plan goes through chin filler. Downturned mouth corners also rob the sense of a full lip; that is why the lip is often planned together with the mouth corners.
What is the role of botulinum toxin in thin lips?
In patients who invert the upper lip when smiling, the vermilion "disappears" in the smile even if it exists at rest. Some professionals use botulinum toxin in the orbicularis oris muscle to reduce that inversion and show more vermilion.
Points of attention, at a review level:
- The toxin does not create volume: it changes the lip dynamics, not the size.
- It can interfere, temporarily, with functions such as sipping through a straw, whistling, drinking and articulating some sounds.
- It can be combined with filler, at the professional's discretion, when both causes are present.
The fundamentals of the product are in botulinum toxin in orofacial harmonization.
Which risks weigh most in thin lips?
Thin lips carry the same risks as any lip filler, with some aggravating factors:
- Visible or palpable product, because of the little covering tissue.
- Migration past the vermilion border, especially when a lot of volume is sought at once.
- Excessive projection of the upper lip, the "beak" look.
- Significant swelling in the first few days, which can frighten the patient.
- Vascular occlusion, because the superior labial and inferior labial arteries run within the lip itself, with a variable course.
Use a specific consent form for lips; there is a lip filler informed consent template that can be adapted.
How to align the patient's expectations?
People with thin lips usually arrive with a reference photo of someone with naturally full lips. The conversation needs to translate the request into something possible in that patient's tissue.
- Ask what bothers them: volume, contour, asymmetry, a lip that disappears when smiling.
- Explain the cause found in the assessment, including what is not about volume.
- Propose stages: starting conservative and completing at a follow-up usually gives a more natural result in thin lips.
- Agree on what is not promised: a lip identical to the photo, absolute symmetry, no swelling.
How do thin lips appear in Harmy?
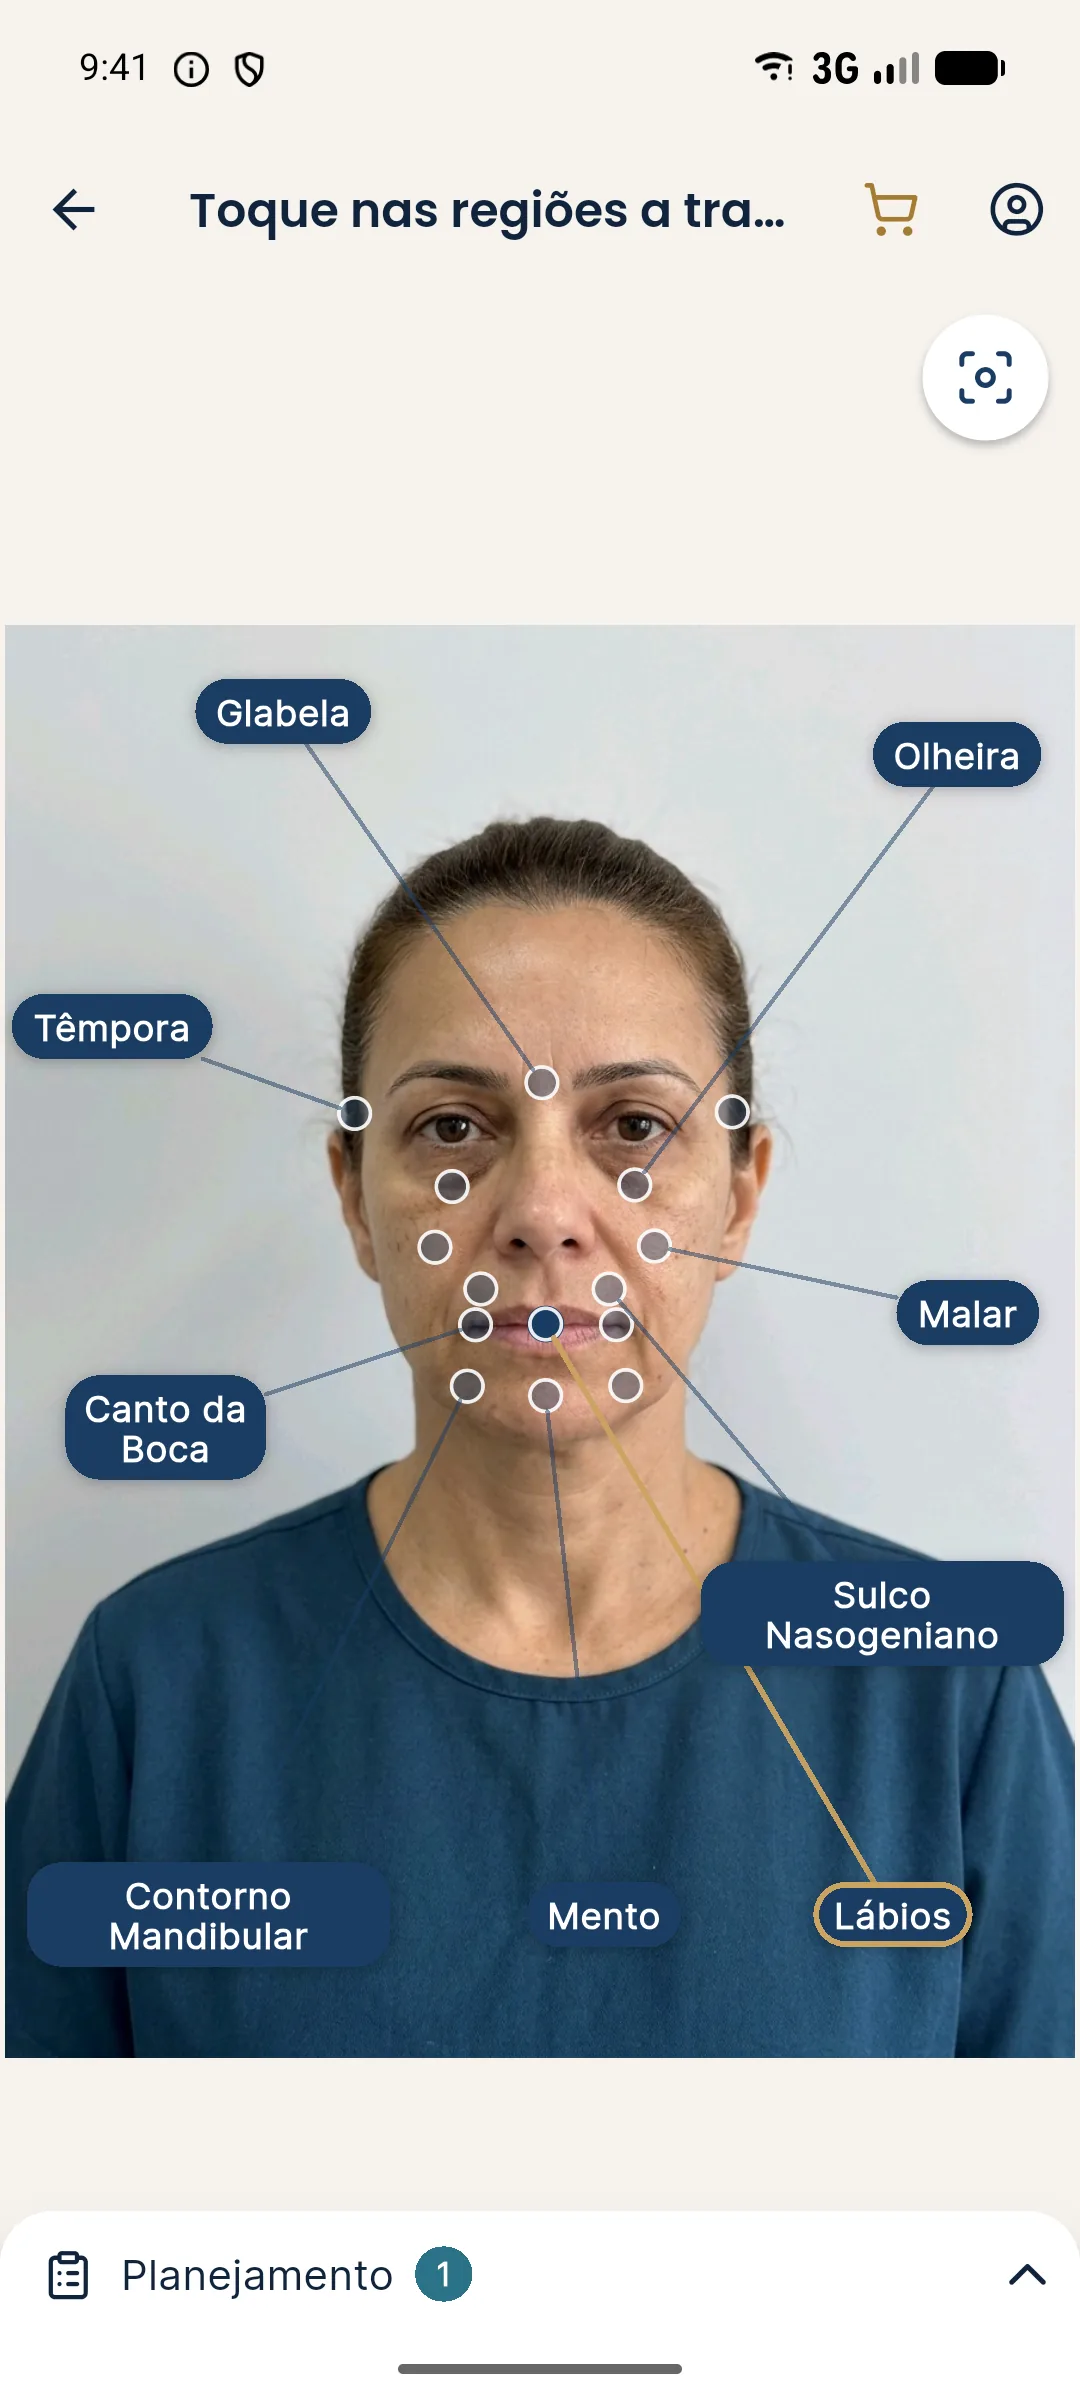
The projection is an illustrative simulation, not a promise of results, and it does not represent causes that filler does not treat, such as lip length. To guide that conversation, see how to present before and after in the consultation.
Thin lip assessment checklist
- Main cause identified (constitutional, aging, length, support, dynamics).
- Upper and lower lip proportion and mouth width recorded.
- Incisor exposure at rest and upper lip height observed.
- Dental support assessed or referred.
- Profile analyzed, with nose and chin.
- Standardized photos at rest and smiling.
- Staged plan and expectations agreed in writing.
- Hyaluronidase available and history of cold sores recorded.
Frequently asked questions
Does filler fix thin lips?
It depends on the cause. When the lip is thin because of little vermilion volume and there is tissue to receive product, filler usually helps. When the cause is a long upper lip, lack of dental support or lip inversion when smiling, filler alone tends to fall short or look artificial.
How much hyaluronic acid is used in thin lips?
Thin lips usually call for conservative volumes and, often, more than one session, because the tissue accepts little product at a time. The amount is defined by the licensed professional, after assessment.
Does botulinum toxin make thin lips bigger?
It does not increase volume. In some patients who turn the upper lip inward when smiling, the toxin can reduce that inversion and show more vermilion, with possible effects on lip function. The indication is assessed case by case.
Why did my lips get thin with age?
With aging, the lip loses volume, the upper lip tends to lengthen and the support from the teeth and bone changes. The result is less visible vermilion and more skin between the nose and the mouth.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.