
Cheek Sagging Over the Jaw: What Blurs the Contour

 BeforeSimulation
- Highlighted area
Quick facts
- Concern
- The cheek descends and covers the jawline, blurring the contour
- Structures
- Jowl, pre-jowl sulcus, mandibular and masseteric ligaments
- Plan logic
- Support from above before filling below
- Risk of error
- Volume in the jaw without treating the descent can weigh down the lower third
The contour of the jaw depends on a clean, continuous line that separates the face from the neck. When the cheek descends and settles over that line, the contour becomes wavy, the jaw disappears and the face looks "dropped." In general, patients talk about a "double chin" or a "sagging cheek," but what they describe is jowl: the accumulation of fat and skin beside the chin.
This page explains the mechanism and the logic of the plan. It connects with drooping jawline, sagging cheeks and defined jaw.
Why does the cheek descend over the jaw?
The face is held up by layers, and fat descent is a phenomenon with several causes. The main ones:
| Factor | Role | Result |
|---|---|---|
| Loss of midface volume | Reduces the support of the fat | The cheek descends toward the contour |
| Loosening of the ligaments | The retaining ligaments, such as the mandibular and masseteric, stretch | The fat shifts downward |
| Fat redistribution | The upper compartments empty and the lower ones accumulate | Jowl and double chin |
| Loss of skin quality | Less collagen and elasticity | Skin less able to hold the fat |
| Bone resorption | The jaw and maxilla lose volume | Less structural support |
| Marked weight loss | Overall volume loss and laxity | More obvious descent |
The mandibular ligament is an anchoring point that separates the jowl from the chin, forming the pre-jowl sulcus. When fat descends, it is "dammed" by that ligament and forms the wave. The layered reasoning is in facial aging by layers.
How to assess
The exam should look at the face from bottom to top and from top to bottom. The cause is usually above the point that bothers the patient.
An extra clue: compare the photo with the patient seated and lying down. Lying down, fat descends less, which reveals how much of the complaint is gravitational.
What harmonization can offer
The general logic is to support from above before filling below. Filling the jaw without treating the descent can make the appearance worse, because it adds volume to a lower third that is already heavy.
Midface. Cheekbone filler restores projection and support of the superficial layers, and can indirectly reduce the descent toward the jowl. See midface ptosis.
Jawline. Jawline filler in selected cases helps redefine the line, especially when there is bone loss. In pronounced jowl, it should come after the upper support or together with it.
Chin. In a recessed chin, chin projection improves the transition between the jowl and the chin. See chin filler.
Skin quality and support. Biostimulators can be considered for skin quality and support in suitable cases. Thread lifts are another option, with their own indications and risks. See PDO threads in the neck and lower third and lower third laxity: assessment.
Localized fat. If the main component is fat, there are approaches for double chin and jowl, with their own indications. See double chin: assessment.
Risks
The risks of filler include swelling, bruising, nodules, asymmetry and irregularities, plus less frequent vascular complications. The jaw area has the facial artery crossing the border, and the marginal mandibular branch of the facial nerve requires anatomical knowledge. Hyaluronidase must be available in hyaluronic acid procedures. In thin, lax skin, the product is more likely to show visible irregularity.
How to show it in Harmy
In Harmy, the Jawline point and the Cheekbone point show, in the frontal photo, the effect of support in the two areas. For this concern, make two projections of the same patient: one with Jawline only and another with Cheekbone and Jawline. The comparison shows that the contour improves more when the midface is part of the plan, which justifies the order.
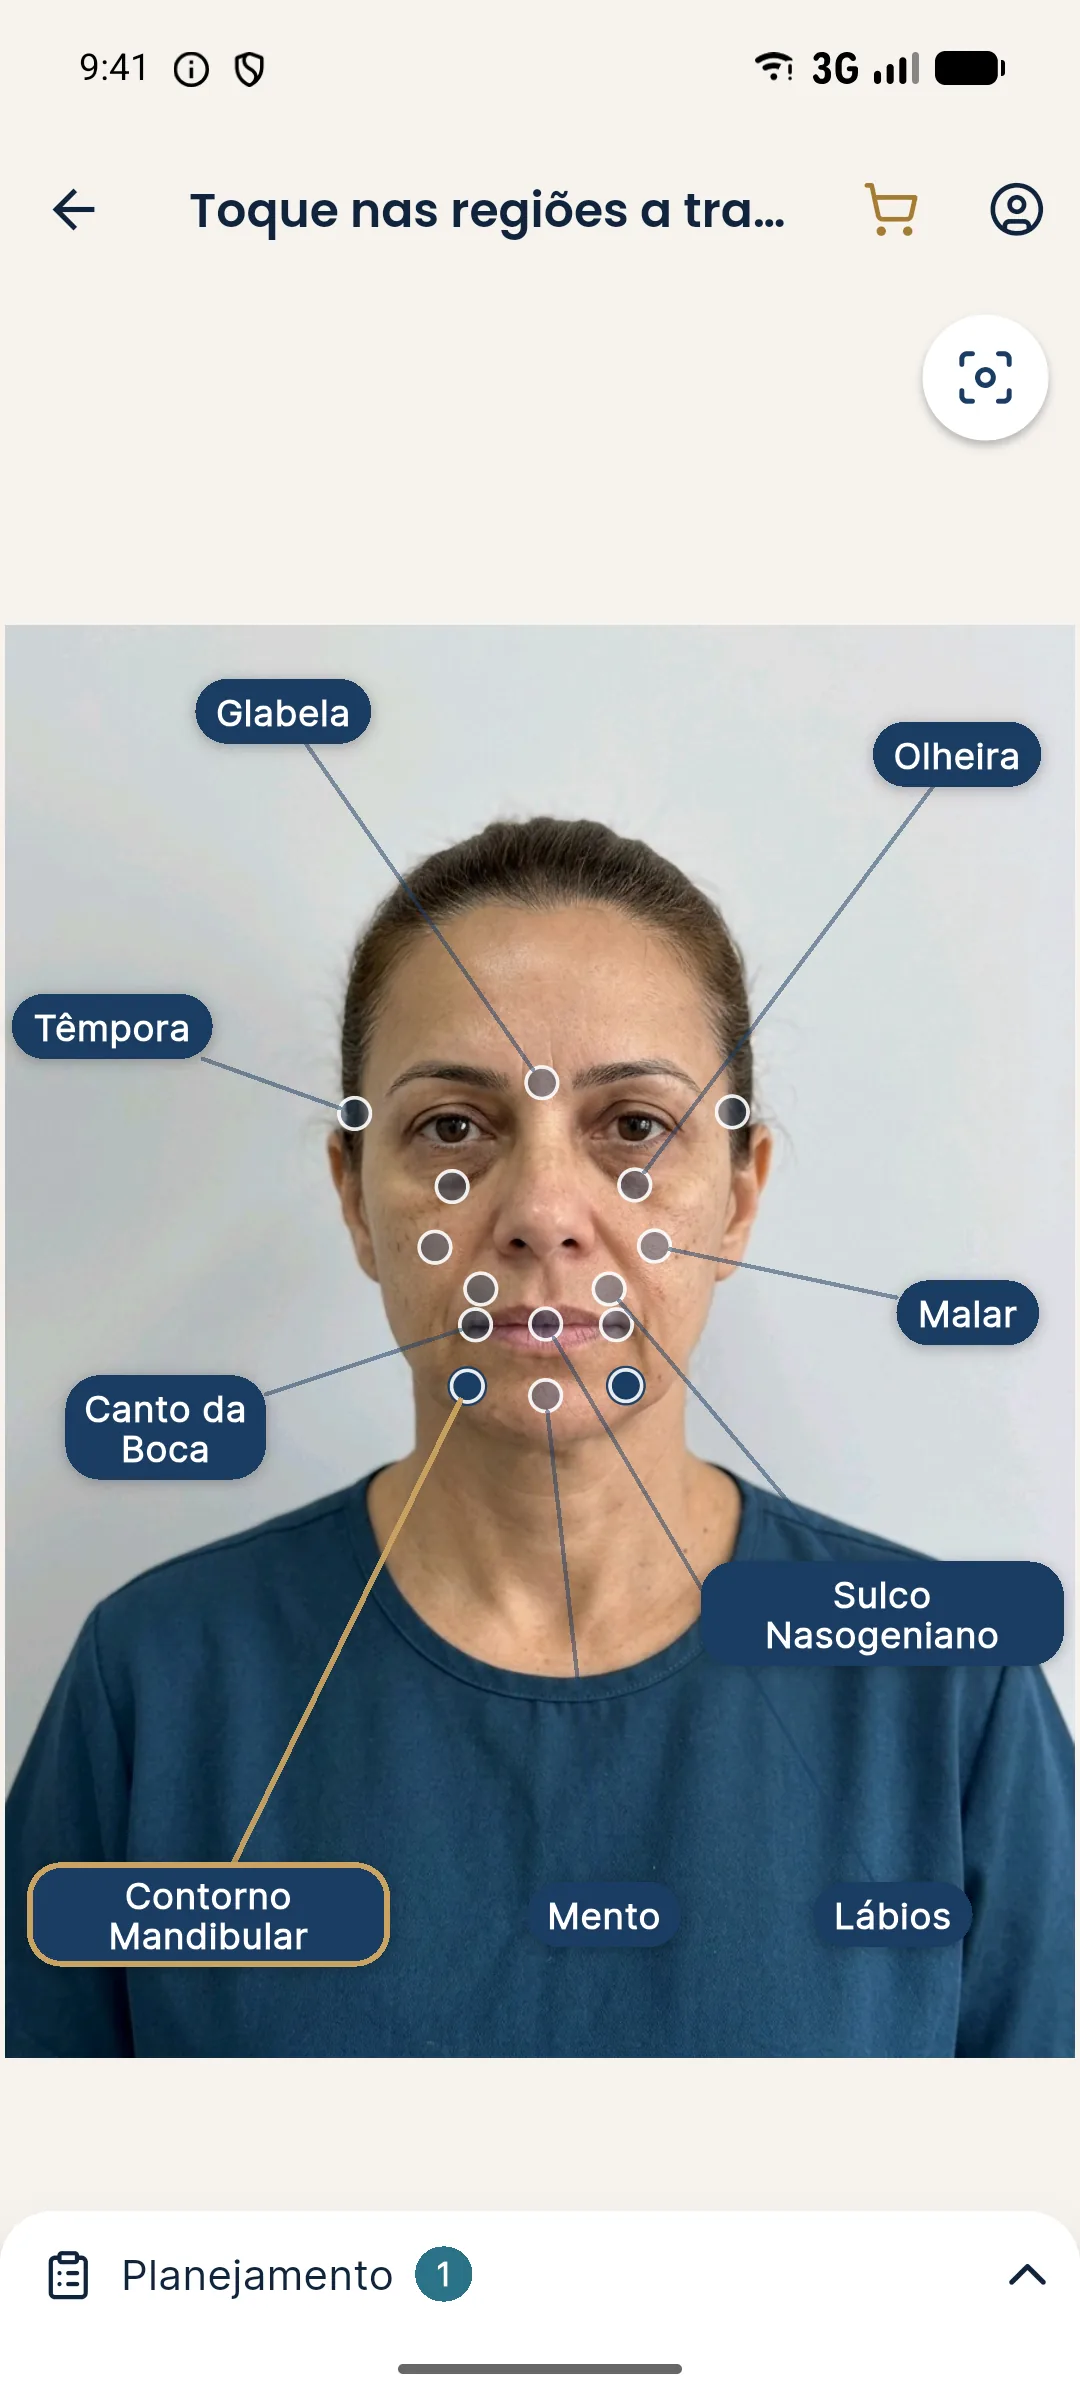
The app changes only what was marked and does not alter skin or lighting. It uses the frontal photo, so the jowl is seen in frontal view; the profile is not part of the simulation. In a bilateral area, the ml is the total, split between the two sides.
Common mistakes in the jowl plan
The most frequent mistake is starting with the jaw. The jowl draws attention below, and the patient points to the contour, but the cause is usually above, in the midface and the ligaments. Filling the jaw first can mask the waviness for a few weeks and later leave the face heavier when the fat keeps descending.
The second mistake is promising too much. Saying that filler will "lift" the jowl creates an expectation the technique does not meet in moderate to significant laxity. The third is ignoring the neck: the lower contour is read together with the neck, and a double chin or platysmal bands can make the result look incomplete. See neck with bands and toxin for platysmal bands. A plan that considers midface, contour and neck, in stages and with honest expectations, is usually the safest.
Wrap-up
Record the assessment, the photos and the plan in stages, with the order justified. For planning reasoning, see jaw and masseter: combining in the plan and cheekbone and jaw: combining in the plan. Volumes and techniques are at the discretion of the licensed professional, in accordance with the rules of their professional council in Brazil.
Frequently asked questions
What is jowl?
It is the accumulation of fat and skin that descends from the cheek and sits above and beside the chin, covering part of the jawline. It tends to appear with age and after weight loss, and leaves the contour wavy.
Does jaw filler fix a sagging cheek?
In some cases it helps define the line, but if the cause is descent of the midface, adding volume to the jaw can weigh down the face. The plan usually starts with upper support, at the professional's discretion.
What is the relationship between the cheekbone and jowl?
Loss of support in the cheekbone and midface contributes to fat descending toward the jowl. Treating the midface can improve the lower contour indirectly.
Can jowl be treated with injectables alone?
It can improve partially in mild to moderate cases. With significant laxity, injectables have limits and other approaches may be discussed.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.