
Sagging face: assessing the layers and options

- Nerve
- Highlighted area
Quick facts
- Concern
- A face that is "falling," with contour, cheek and gaze losing support
- Key insight
- Sagging can be bone, fat, ligament or skin, and each layer calls for a different response
- Supporting measure
- Gentle lift test, oblique photo and comparison with an old photo
- Limit
- Volume provides support, but it does not reposition tissue the way surgery does
"My face is falling" is one of the most common phrases in mature HOF, and one of the most ambiguous. It can describe a cheek that lost height, a contour that lost definition, a more prominent neck or a heavier gaze. The first mistake would be to treat the phrase as a single diagnosis and inject volume in the most visible area.
This page treats the concern layer by layer. You learn to decide whether bone, fat, ligament or skin predominates, to test whether the tissue can be repositioned, and to combine the available options without promising what only surgery delivers. For the cheek angle, see midface ptosis, and for the skin, loose skin on the face.
Which layers explain the sagging face?
The face is a set of layers that age at different rates. The classical reading describes five: bone, ligaments, fat compartments, muscle and skin. The study of the layers of the face and of facial aging by layers organizes the reasoning.
- Bone: resorption of the orbit, maxilla and mandible removes support and increases the space the soft tissues have to fill. See facial bone loss.
- Ligaments: the retaining ligaments anchor the skin to the bone. When they give way, tissue descends between the anchor points.
- Fat: the compartments lose volume or separate, and superficial fat shifts downward. Deep facial fat loss has its own page.
- Muscle: repeated actions and hypertonia mark folds and change the position of the brow and mouth corner.
- Skin: loss of collagen and elastin reduces recoil and leaves the skin loose over its contents.
In each patient, one or two layers dominate. Identifying them is what makes the plan specific rather than generic.
How to test what is repositionable?
The gentle lift test is simple: with the patient seated and relaxed, lift the skin of the cheek and the preauricular region with your fingers toward the bone, and observe. If the face reorganizes and the fold softens, there is a descent component. If it stays hollow and flat, the problem is volume. This test guides the conversation, it does not replace an exam.
| Test or finding | If it improves with the lift | If it does not improve |
|---|---|---|
| Fold beside the nose | Descent predominates | Volume predominates |
| Jaw contour | Skin laxity and jowl | Bone or fat loss |
| Lower eyelid | Cheek descent | Loss of orbital volume |
| Neck | Skin and platysma | Subplatysmal fat |
| Likely response to volume | Partial | More predictable |
To record the result of the test, use photos with the same lighting and distance before and during the lift. Oblique facial analysis is especially useful, because it shows the descent that the frontal photo hides.
What can HOF offer?
HOF works on support, volume and skin quality, not on surgical repositioning of tissue. The options usually discussed are the following, always at the discretion of the qualified professional and according to the rules of their professional council.
- Support filler in the cheekbone and, in selected cases, along the jawline. See cheekbone filler and jawline filler.
- Collagen biostimulator, when the concern mixes loss of skin quality with mild laxity. See biostimulator in the midface and biostimulator along the jawline.
- Thread lift, in selected cases. It has a restricted indication and its own risks, and its role is limited in the face of marked descent.
- Skin treatment with technologies and continuous care, outside the scope of this page.
Every hyaluronic acid injection must take place with hyaluronidase available. In higher vascular risk areas, such as the nasolabial fold and the temples, anatomical attention is greater. Explain the possible complications to the patient, such as swelling, bruising, asymmetry and, rarely, vascular occlusion, and record consent.
How to order the plan?
Start with support and finish with detail. In sagging faces, this means treating the midface or the bony foundation before dealing with the fold, the jowl or the neck. The idea is described in facial skeleton before injecting and in complete midface in the plan. Reassess between stages, because many signs change with support and no longer need direct treatment.
What to tell the patient about the limits?
Be clear from the start: HOF does not "lift" the face the way surgery does. It can improve support, definition and skin quality, and the patient should know that gravity keeps acting. When there are clear signs that the goal requires surgery, offer the referral without awkwardness. The conversation script is in aligning expectations in mature skin and in concerns that HOF does not solve.
How does Harmy help without overpromising?
The app shows a subtle projection, from a frontal photo, and does not reposition tissue. This is useful to illustrate the gain in support at the cheekbone or jawline, and it should come with the notice that the simulation does not represent the effect of gravity or movement.
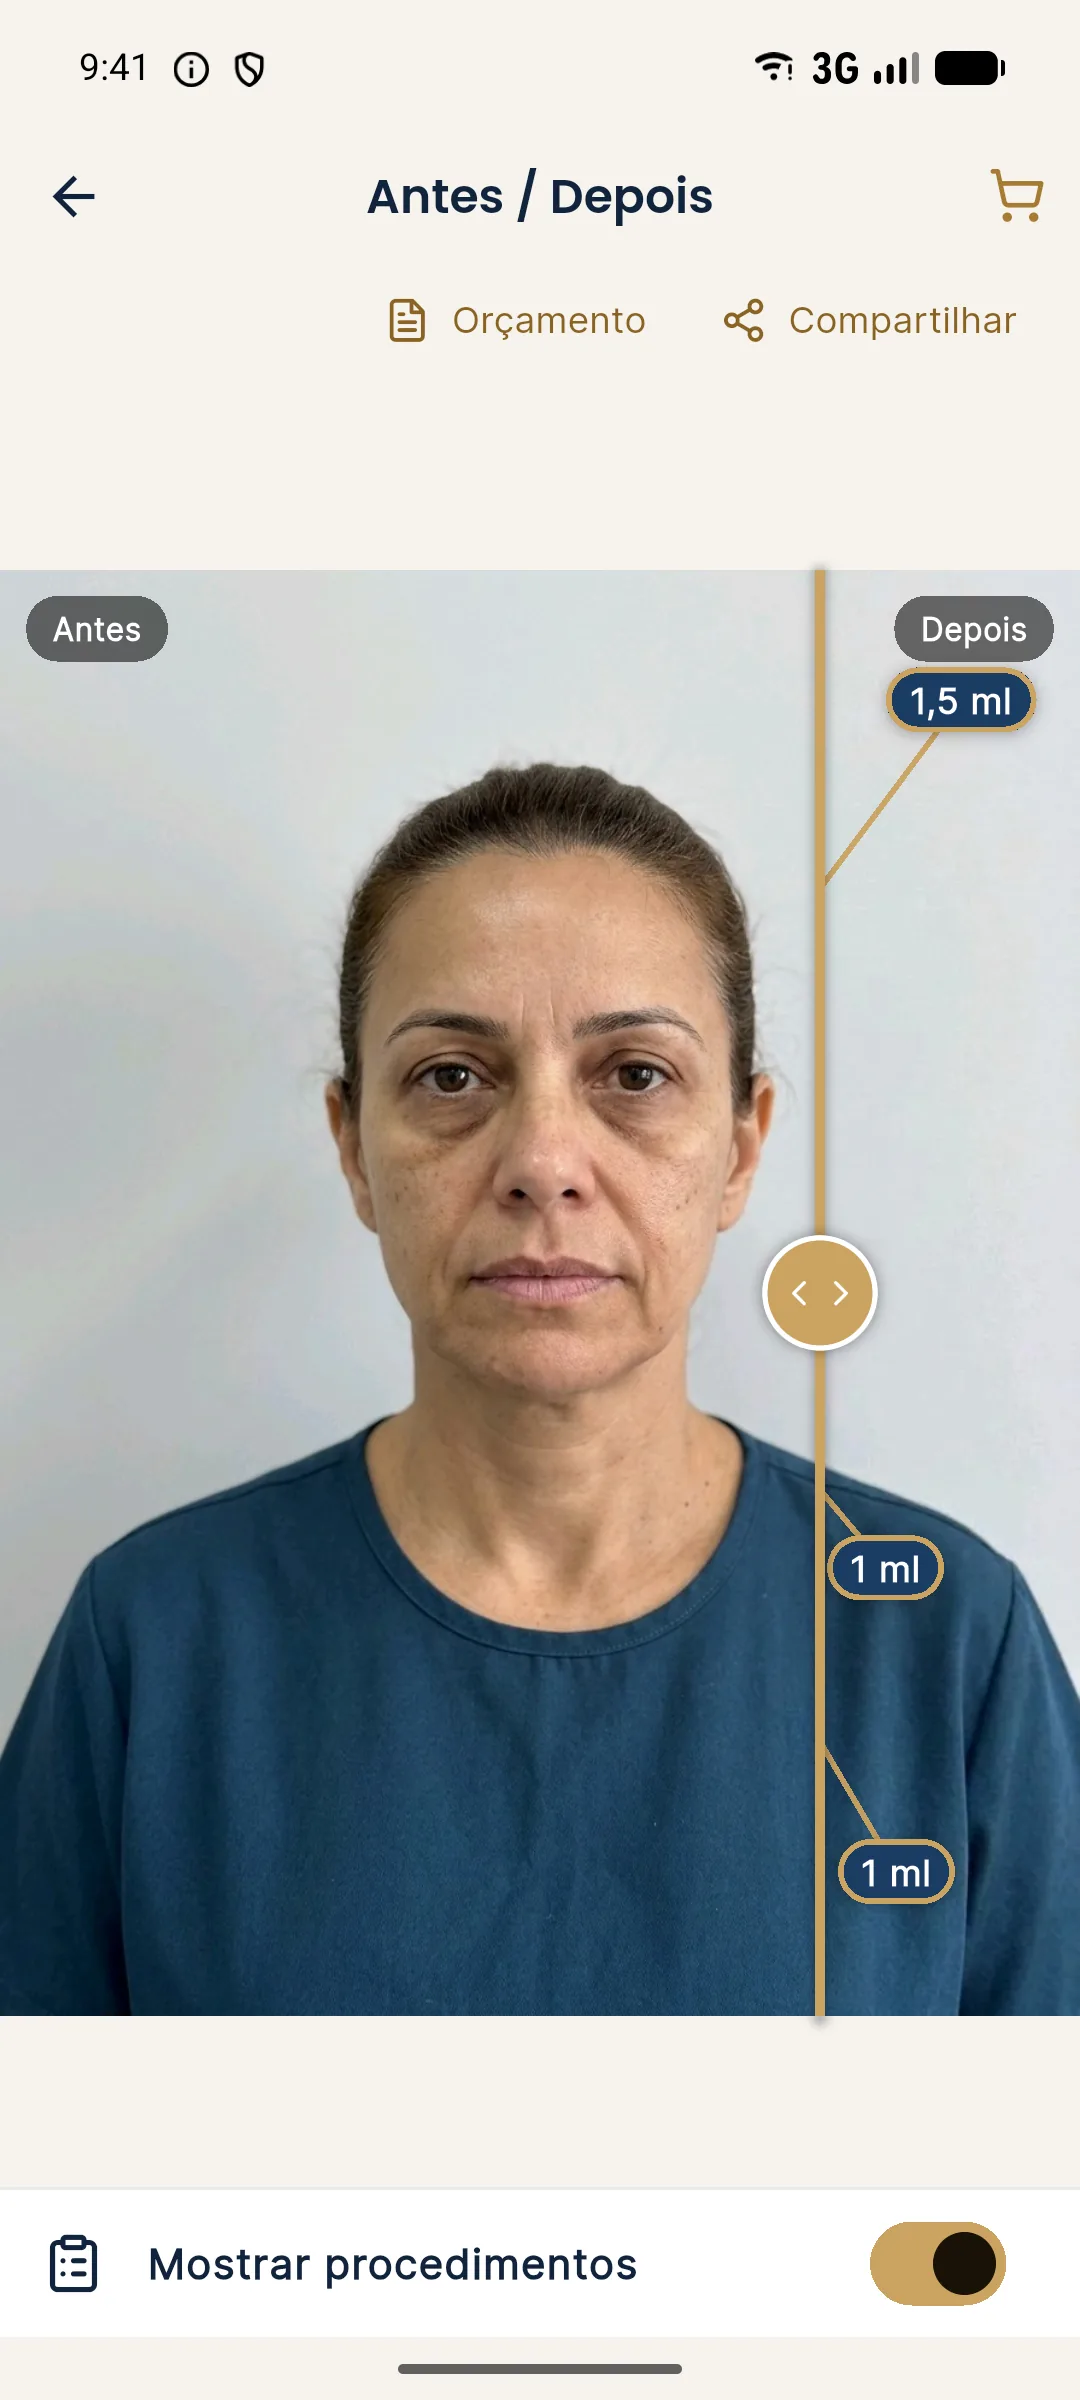
Use the feature that shows the treated areas to explain to the patient where each ml was planned, and presentation mode to turn the screen with the slider in full screen. Record the plan per patient in the history to compare the effect at follow-ups.
Frequently asked questions
Why does the face sag over time?
Because several layers change together: bone resorbs, fat loses volume and descends, ligaments loosen and skin loses elasticity. The weight of each factor varies from person to person.
Does filler lift a sagging face?
It can improve the support and appearance of the treated area, but it does not play the role of a facelift. With marked descent, the effect tends to be limited.
Do collagen biostimulators or threads fix laxity?
They are options for skin quality and support in selected cases, at the discretion of the qualified professional, after assessment. None guarantees a result, and the indication depends on the degree of laxity.
When is surgery the best alternative?
When there is excess skin or marked descent, so that volume would only displace the problem. In those cases it is worth discussing a referral.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.