
Facial Analysis After 60: Realistic Goals in the Plan
Quick facts
- Focus of the age group
- Realistic goals, safety and the few areas with the most visual return
- Typical signs
- Advanced laxity, thin skin, bone resorption and deep folds
- Planning risk
- Promising more than the tissue allows and piling on volume to compensate for laxity
- The plan's ally
- Frank conversation, short stages and frequent reassessment
The patient who arrives after 60 usually brings a mix of desire and apprehension: they want to improve but fear "looking different". They also know their own face well and have often seen the results of procedures on acquaintances. For the professional, the challenge of the analysis is to translate that request into goals the tissue can deliver, safely and without erasing identity.
This page covers the analysis and the plan for this age group: what to observe, what to prioritize, when to propose less and how to talk about limits. It complements facial analysis at 50 and the specific plan for facial harmonization over 60. The general clinical context is in facial harmonization in patients over 50.
What does age change in the analysis?
It is not age itself, but what it tends to bring: tissue with less reserve, thinner skin, less fat in some compartments and more laxity in others, and a resorbed bone framework. Added to this is the rise in comorbidities and in long-term medications.
| Aspect | Why it matters in the plan | What to do |
|---|---|---|
| Thin, lax skin | Shows irregularities and tolerates little volume | Prefer short stages and assess the tissue at every session |
| Bone resorption | Lack of deep support makes volume "slide away" | Consider structure before detail |
| Advanced laxity | Volume alone does not lift | Discuss limits and other approaches |
| Medications | Anticoagulants and others change the bruising risk | Detailed medical history, see anticoagulants and injectable procedures |
| Expectation | May come from old photos or unrealistic references | Align observable goals from the first conversation |
How to take the medical history and assessment with more care?
The medical history deserves extra time: chronic diseases, previous facial surgeries, use of anticoagulants and antiplatelets, immunosuppressants, history of herpes, reactions to products and previous fillers, including those the patient cannot name. Cases with an unknown product call for extra attention, as in patient with unknown previous filler.
Some situations call for postponing or revising the plan. The general list is in general contraindications in facial harmonization, and autoimmune diseases have their own page: autoimmune diseases and fillers. Consent should be explained calmly, in plain language, and the informed consent signed with time for questions.
Suspicious skin lesions are not a facial harmonization matter: refer for dermatological assessment before any procedure in the area.
Which areas usually give the most visual return?
There is no single answer, but there is a line of reasoning: areas that support and organize the face give more return than those that treat details. In many cases, the conversation revolves around a few areas.
- Midface and cheekbone: supports the cheek and the gaze. The proportion of volume is always conservative, because the tissue has already descended. See ideal cheekbone projection.
- Contour and jawline: helps reorganize the transition between face and neck. See lower face laxity.
- Chin: when there is retrusion, improves profile balance, as in plan to balance the profile.
- Lips: the goal is usually hydration and discreet definition, not enlargement. The patient who asks for full lips at 60 deserves a frank conversation.
- The eyes: the periorbital area calls for a specific assessment, and not every dark circle responds to filler. See dark circles: types and assessment.
How to talk about limits without discouraging?
The most delicate point in this age group is the conversation. Older patients tend to listen carefully and take what the professional says seriously. That is why stating clearly what the procedure can and cannot do is part of care, and protects against dissatisfaction later.
Three language points help:
- Speak in "can" and "tends to", without fixing the result.
- Show the plan in stages, with an order of priority.
- Leave the door open to stop, and record it.
If the expectation does not fit the tissue, the path is to reduce the plan, propose other approaches or, when necessary, not to recommend anything. See when to say no to the aesthetic plan and facial harmonization plan and patient mental health.
What does Harmy show and what does it not show?
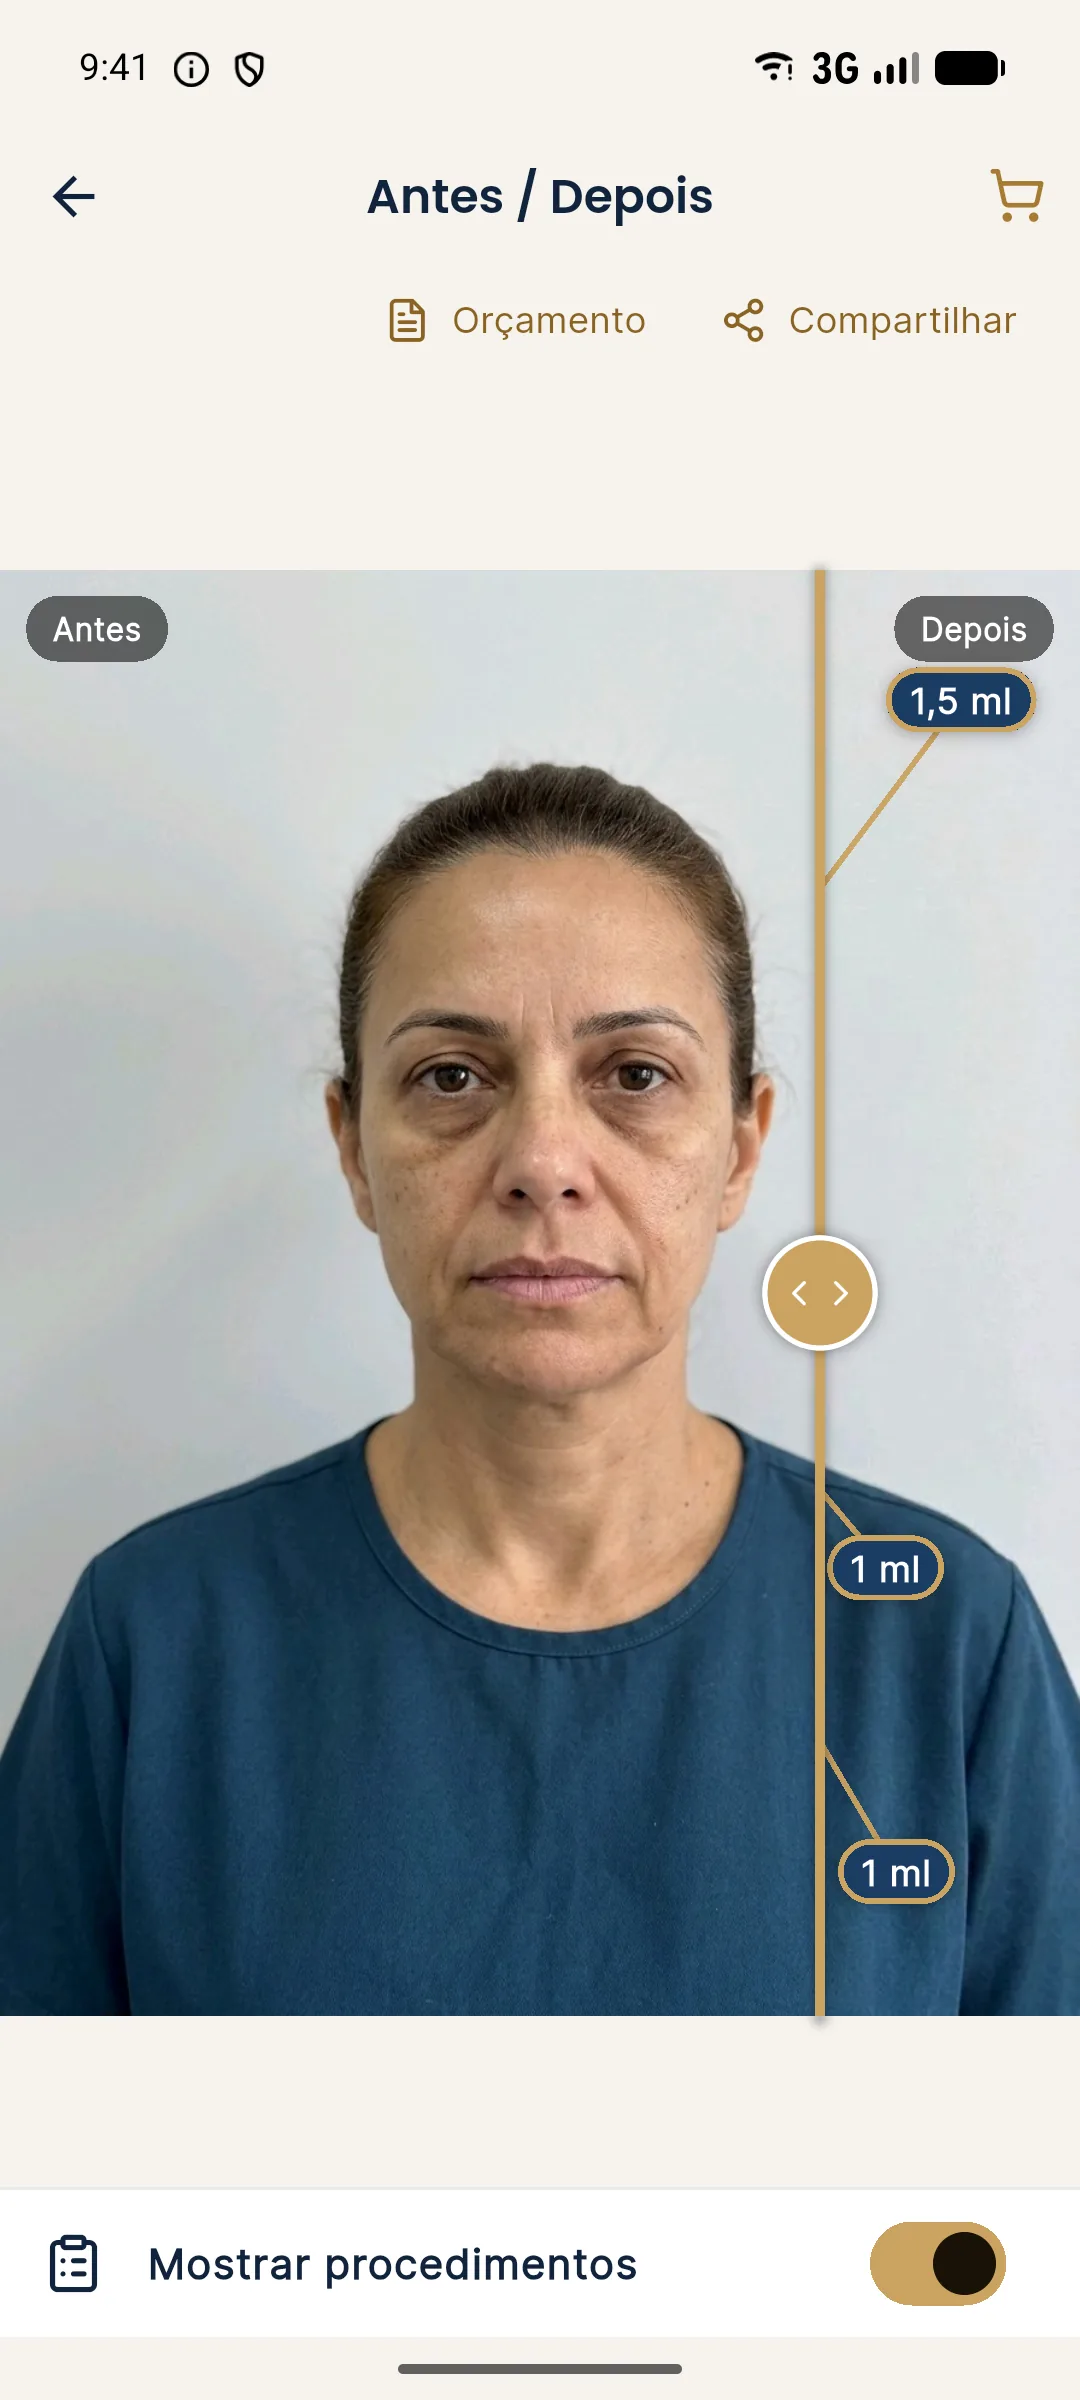
Use the simulation with more care in this audience: if the projection looks "too good", it creates an expectation the tissue will not meet. That is why the Subtle or Moderate intensity usually makes more sense than Pronounced, at the professional's discretion. The tool's limits are in limits of 2D simulation and in explaining that simulation is not a guarantee.
How to organize stages and safety?
Short stages let you see how the tissue responds before continuing. Keep the complication protocol at hand, hyaluronidase available when the procedure uses hyaluronic acid, and a clear contact channel afterward. Reinforce with the patient, and with a family member if they wish, the warning signs: disproportionate pain, paleness or darkening of the skin, vision changes and fever call for immediate contact.
Record everything in the patient record and remember that the decision on product, volume and technique belongs to the licensed professional, according to the rules of their professional council.
Frequently asked questions
Can facial harmonization be done after 60?
In many cases yes, as long as there is an individual assessment, a careful medical history and realistic goals. Age alone does not decide: health status, medications and tissue quality count.
Which areas usually give the most visual return after 60?
Usually the midface, the jawline, the chin and, with caution, the lip area. The choice depends on each face and is the decision of the licensed professional.
Why does the plan after 60 need to be more conservative?
Thinner skin, greater laxity and the possible use of medications that affect bleeding call for caution. Too much volume over tissue that has already descended can weigh the face down.
When is it better not to recommend anything for a patient aged 60 or older?
When the expectation is incompatible with what the tissue allows, when there is a contraindication, or when the reason for the request lies outside the face. Saying no, or proposing less, is part of planning.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.