
Toxin or filler first: which order to follow in the plan

 BeforeSimulation
Quick facts
- Central question
- Does the concern come from movement (muscle) or from loss (volume)?
- If it is movement
- Toxin usually goes first, because it reduces the force that creases the skin
- If it is volume
- Filler usually goes first, because it restores support
- If it is both
- Split into stages and reassess the response to each tool
- Who decides
- Qualified professional, after assessment
The question "toxin or filler first?" comes up in almost every plan that involves lines and volume at the same time, especially in the upper and middle thirds of the face. The answer is not in a fixed rule but in the cause of the concern. This page organizes the arguments for each order, shows a decision table and explains how the simulation fits into the conversation. The final approach depends on the qualified professional, according to the rules of their professional council, and there is no technique protocol here.
What is the question that decides the order?
Ask: does this mark come from movement or from loss? If the patient creases because the muscle contracts hard, the mark is dynamic and botulinum toxin usually enters the reasoning. If the mark is there at rest because the tissue lost volume or support, hyaluronic acid usually enters. Many faces have both components, and that is where order matters.
The distinction between dynamic lines and static lines is the first filter. Dynamic lines appear with expression; static lines remain with the face relaxed. Ask the patient to relax, then to frown, and compare. What disappears at rest and shows up in movement is dynamic; what persists is static or mixed.
Why start with toxin?
There are three common arguments for putting toxin first, when there is a significant muscle component:
- It reduces the force that repeats the mark. If the muscle keeps creasing, any filler in the fold can be "pushed" or deformed by movement.
- It shows what is left. After the toxin takes effect, what stays marked is the static component, and the volume decision is more honest.
- It protects the investment. Filling a line that still creases hard may take more product and last less.
This applies mainly to the glabella and forehead. The counterpoint is the usual one: in a short forehead or a heavy eyelid, relaxing too much can weigh down the eyes, and the reasoning changes. See glabella and forehead: combining in the plan and short or long upper third.
Why start with filler?
The arguments for putting filler first appear when the main cause is loss of support or volume:
- It acts on the cause. A cheekbone without support or a hollow temple is not solved by muscle relaxation.
- It changes how the whole face reads. Restoring support to the midface can soften folds and tear troughs without touching the creases.
- It avoids a false solution. Using toxin for a volume concern may only bring a motionless look, without improving the original reason.
This applies to the temples, cheekbone, chin and, in part, the nasolabial fold. See temples and brow and nasolabial fold and cheekbone.
Decision table
| Main concern | Most likely cause | Order that usually enters the conversation |
|---|---|---|
| Frown lines (glabella) | Muscle action | Toxin first; filler only if a static mark remains |
| Horizontal forehead lines | Frontalis action | Toxin with caution; mind the brow position |
| Tired look with hollow temple | Loss of lateral volume | Conservative filler first |
| Flattened cheek and deep fold | Loss of support | Filler for support first |
| Deep mixed mark | Muscle and tissue | Toxin first, reassess, then filler |
| Patient without time for several sessions | Logistics | Discuss risks and decide whether combining is worth it; see a two-session harmonization plan |
The table is an aid to reasoning, not a protocol. Exceptions are common and depend on the exam.
Which risks change depending on the order?
With toxin, the concerns are asymmetry, brow or eyelid drop, headache and swelling, all temporary. With filler, swelling, bruising, asymmetry, nodules and, rarely and seriously, vascular occlusion, especially in the glabella, nasolabial fold, temples, nose and tear trough. When hyaluronic acid is used, hyaluronidase must be available on site.
Doing both in the same session adds time, discomfort and variables. If something happens, it is harder to know which intervention caused the reaction. Separating into stages makes it easier to read. See safety and complications, overview and vascular danger zones of the face.
What interval should there be between one tool and the other?
There is no single interval. Many professionals wait for the toxin to take full effect before reassessing, and only then decide on the volume. This usually takes a few weeks. Others prefer to combine them on the same day in simple cases. The decision is the professional's, based on the case, the risk and the patient's logistics. What matters is recording the order chosen and the reason, so the follow-up has a reference.
For the general cadence, see interval between sessions in the harmonization plan and maintenance: toxin, filler and biostimulator.
How does the Harmy simulation fit in?
In Harmy, you mark the areas on the frontal photo and set the ml and the intensity (Subtle, Moderate or Pronounced). The app does not distinguish the product: it simulates the look of the marked area with the volume entered. For the glabella, the unit is symbolic. That is why the projection serves to show the visual effect of a volume adjustment, not to choose between toxin and filler.
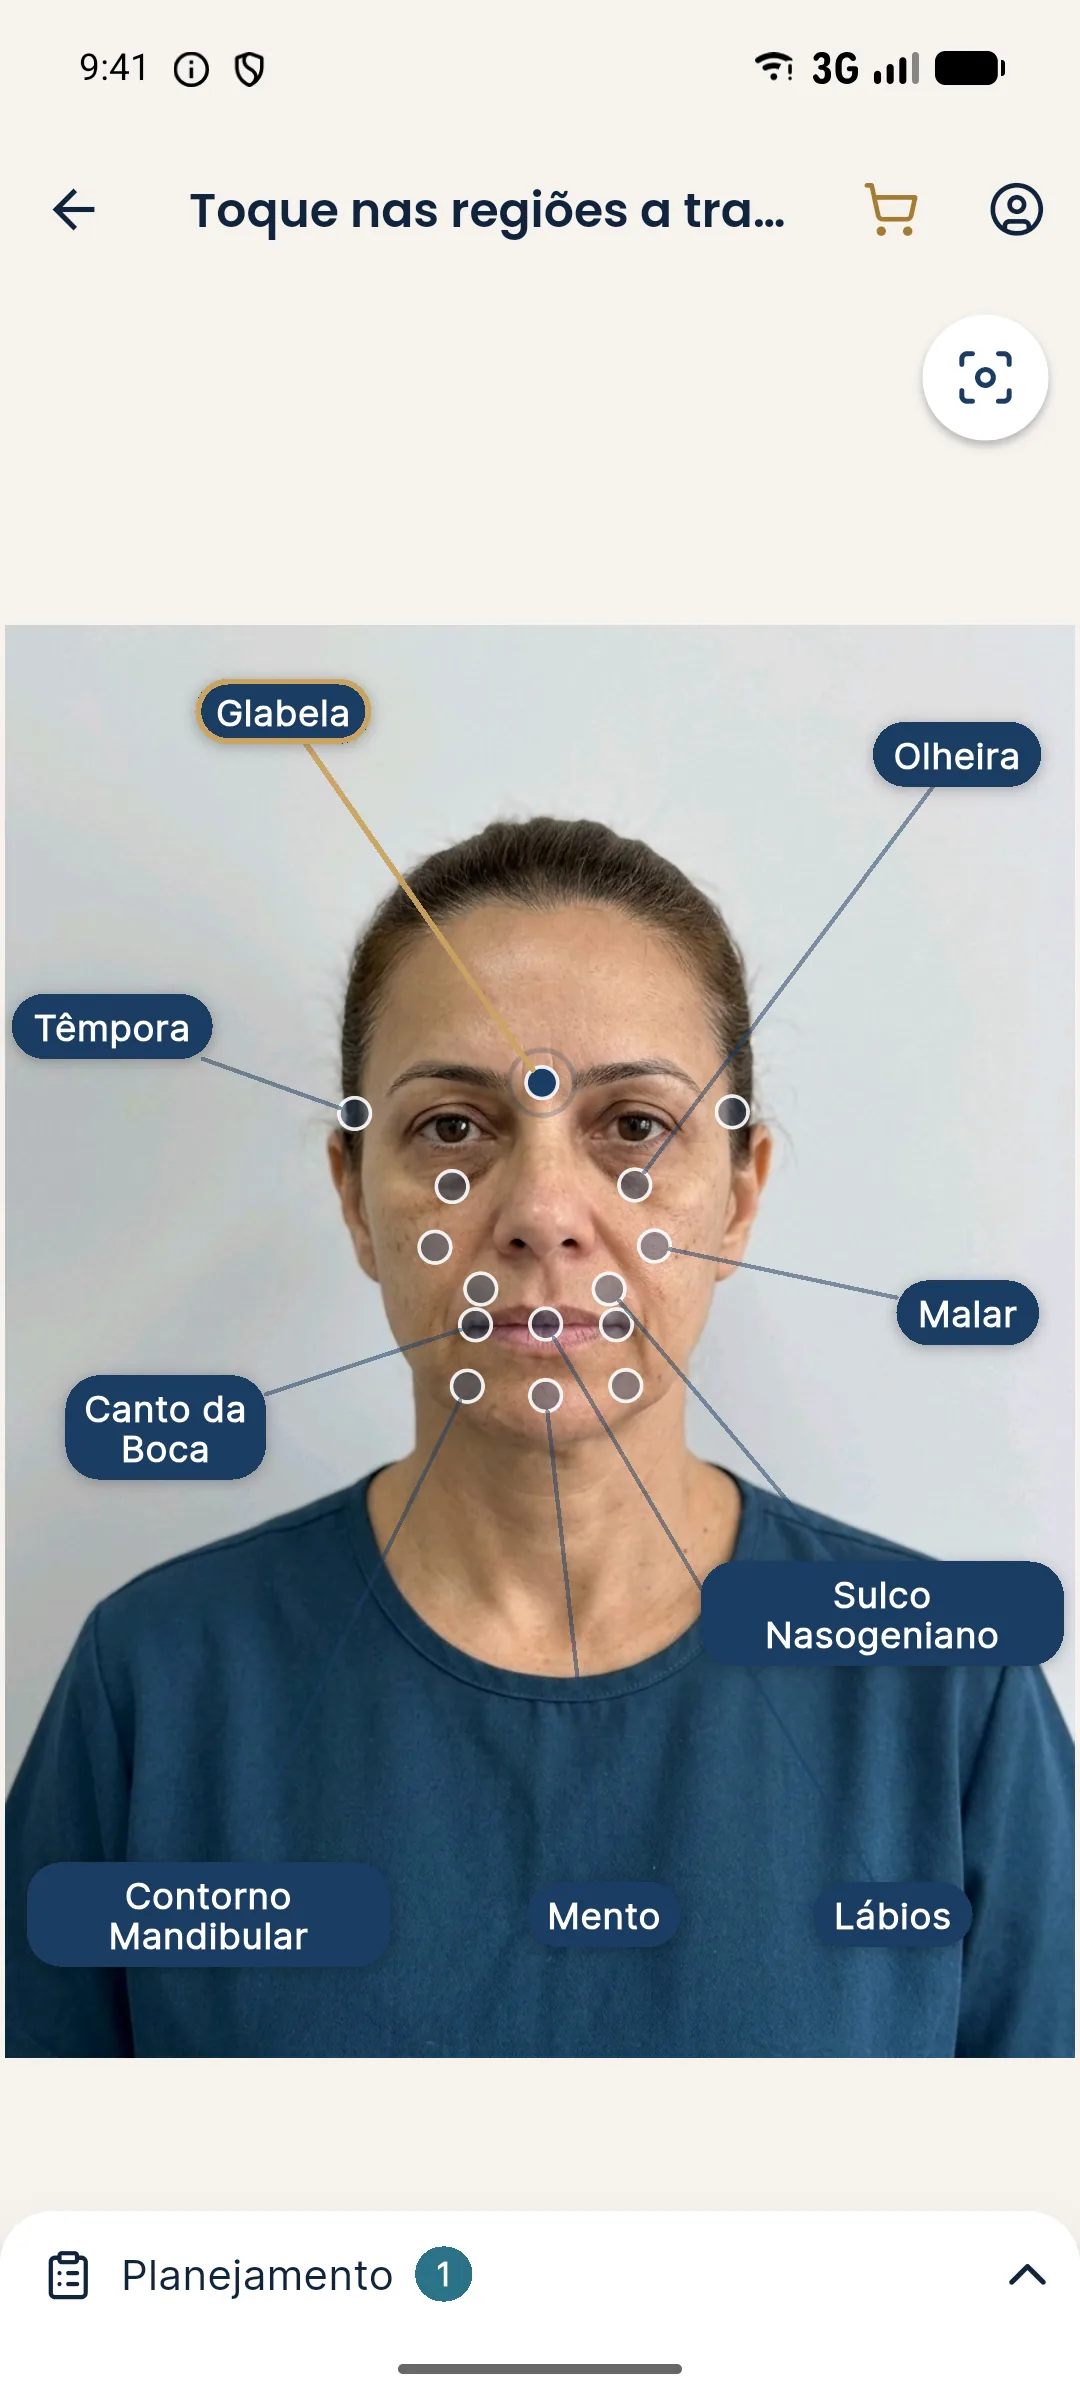
A practical use is to show the difference between marking only the support (for example, cheekbone or temple) and also marking the glabella, to explain why the order matters. For bilateral areas, the ml is the total, split between both sides. The AI respects the volume and changes only what was marked, without simulating muscle action. It is an illustrative simulation, not a promise of results.
See also limits of 2D simulation.
What to tell the patient?
The line explains the logic without promising a result. If the patient arrives with a ready request ("I only want filler here"), ask permission to examine and explain the reason for the suggested order. If they insist on another order, record the decision in the patient record. See patient approval of the plan.
Check before defining the order
Quick review
Summary
The order between toxin and filler comes from the cause of the concern: movement calls for toxin, loss calls for volume, and mixed cases call for stages with reassessment. Record the reasoning, respect the risks of each tool and use Harmy's simulation as a conversation aid, knowing that it does not tell products apart or simulate muscle action.
Frequently asked questions
Toxin or filler: which comes first?
It depends on the cause. When the concern is movement, toxin usually goes in first. When it is loss of volume, filler. There is no universal order.
Can I do both in the same session?
It is possible, and many professionals do. But when the response to one tool changes the decision about the other, splitting into stages allows you to reassess.
Does toxin get in the way of filler or the other way around?
They act through different mechanisms. What matters is the order of reasoning and the interval the professional chooses, not an incompatibility between them.
Does Harmy simulate toxin and filler?
Harmy simulates the volume and look of the marked areas, such as Glabella and Temple. It does not distinguish the product used or simulate muscle action.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.