
Temples and eyebrow: effect on the gaze in the plan

 BeforeSimulation
- Nerve
- Highlighted area
Quick facts
- Topic
- Relationship between the temple and the position of the eyebrow tail
- Core mechanism
- A concave temple leaves the lateral eyebrow unsupported and heavy
- Allies of the plan
- Conservative temporal filler and, when indicated, toxin in the periorbital region
- Caution
- Delicate vascular area, low volume and reviewed anatomy
- Who decides
- A licensed professional, after assessment
Many patients say their gaze looks "heavy" or "drooping" and point to the eyebrow. In a good share of those faces, what you see in the eyebrow has to do with what is next to it: the temple. When the temporal fossa loses volume, the lateral third of the eyebrow is left without support and the shadow grows at the outer corner of the eye. This page shows how the relationship between temple and eyebrow fits into the facial harmonization plan, without becoming a protocol and without promising that the gaze will "open up."
Why does the temple affect how the eyebrow reads?
The eyebrow does not float: its lateral portion rests on the bone and soft tissue of the temporal region. When the temple is full, the transition between the forehead, the eyebrow tail and the lateral face is smooth. When it is concave, a depression appears that "pulls" the reading downward, and the lateral corner of the eye looks burdened. The thin skin of the area accentuates the shadow contrast even more.
This does not mean the eyebrow is actually lower. Measuring with an instrument or photographing with a reference ruler helps confirm it. The ideal position and the parameters used in the analysis are in ideal eyebrow position in planning, and the relationship with the eye corner in gaze tilt and the lateral canthus.
What else can be weighing down the gaze?
Before deciding anything about the temple, rule out other causes. The list below organizes the reasoning without exhausting the subject.
| Possible cause | What you see | Area in the plan |
|---|---|---|
| Temporal concavity | Lateral shadow, unsupported eyebrow | Temple |
| Muscle action of the upper third | Eyebrow pulled down or asymmetric | Toxin, at the professional's discretion |
| Excess upper eyelid skin | Fold covering the lashes | Specific assessment, possible referral |
| Volume loss in the midface | Downward gaze, pronounced tear trough | Cheekbone and tear trough |
| True eyebrow ptosis | Genuinely low position | Medical assessment; treatment beyond the reach of filler |
The distinction between ptosis and volume loss is in ptosis or volume loss: which to treat. In some cases, the patient needs another approach besides facial harmonization, and saying so clearly is part of informed consent.
Where does toxin come into this conversation?
The eyebrow tail responds to the action of the orbicularis oculi and frontalis muscles. In some patients, toxin in the periorbital region and the glabella, at the professional's discretion, changes the balance between the forces that pull down and those that lift, and the eyebrow may look better positioned. This is not a protocol on this page: it is a reminder that temple filler is not the only tool in the reasoning.
For those planning both, order matters. If toxin is going to be used, assessing its effect before deciding the temporal volume avoids stacking two interventions for the same goal. See toxin or filler first: what order in the plan and glabella and forehead: combining in the plan.
What risks weigh on the temple?
The temporal fossa has vessels of significant caliber, and vascular occlusion, although rare, is a serious complication. Bruising and swelling appear more easily because of the skin thickness. Irregularities and asymmetry are also reported. When hyaluronic acid is used, hyaluronidase must be available, and the professional needs to know how to recognize warning signs. The review is in temporal anatomy for injectables and vascular danger zones of the face.
For all these reasons, the volume discussed in the plan is usually low and divided. The logic of starting with little and reassessing is in conservative volume in the first session.
How do you simulate in Harmy without creating a false promise?
In Harmy, you mark the Temple point on the frontal photo, choose the ml and the intensity (Subtle, Moderate or Pronounced) and create the projection. For a bilateral area, the ml entered is the total, split between the two sides. The AI respects the volume and changes only what was marked, so the change is subtle.
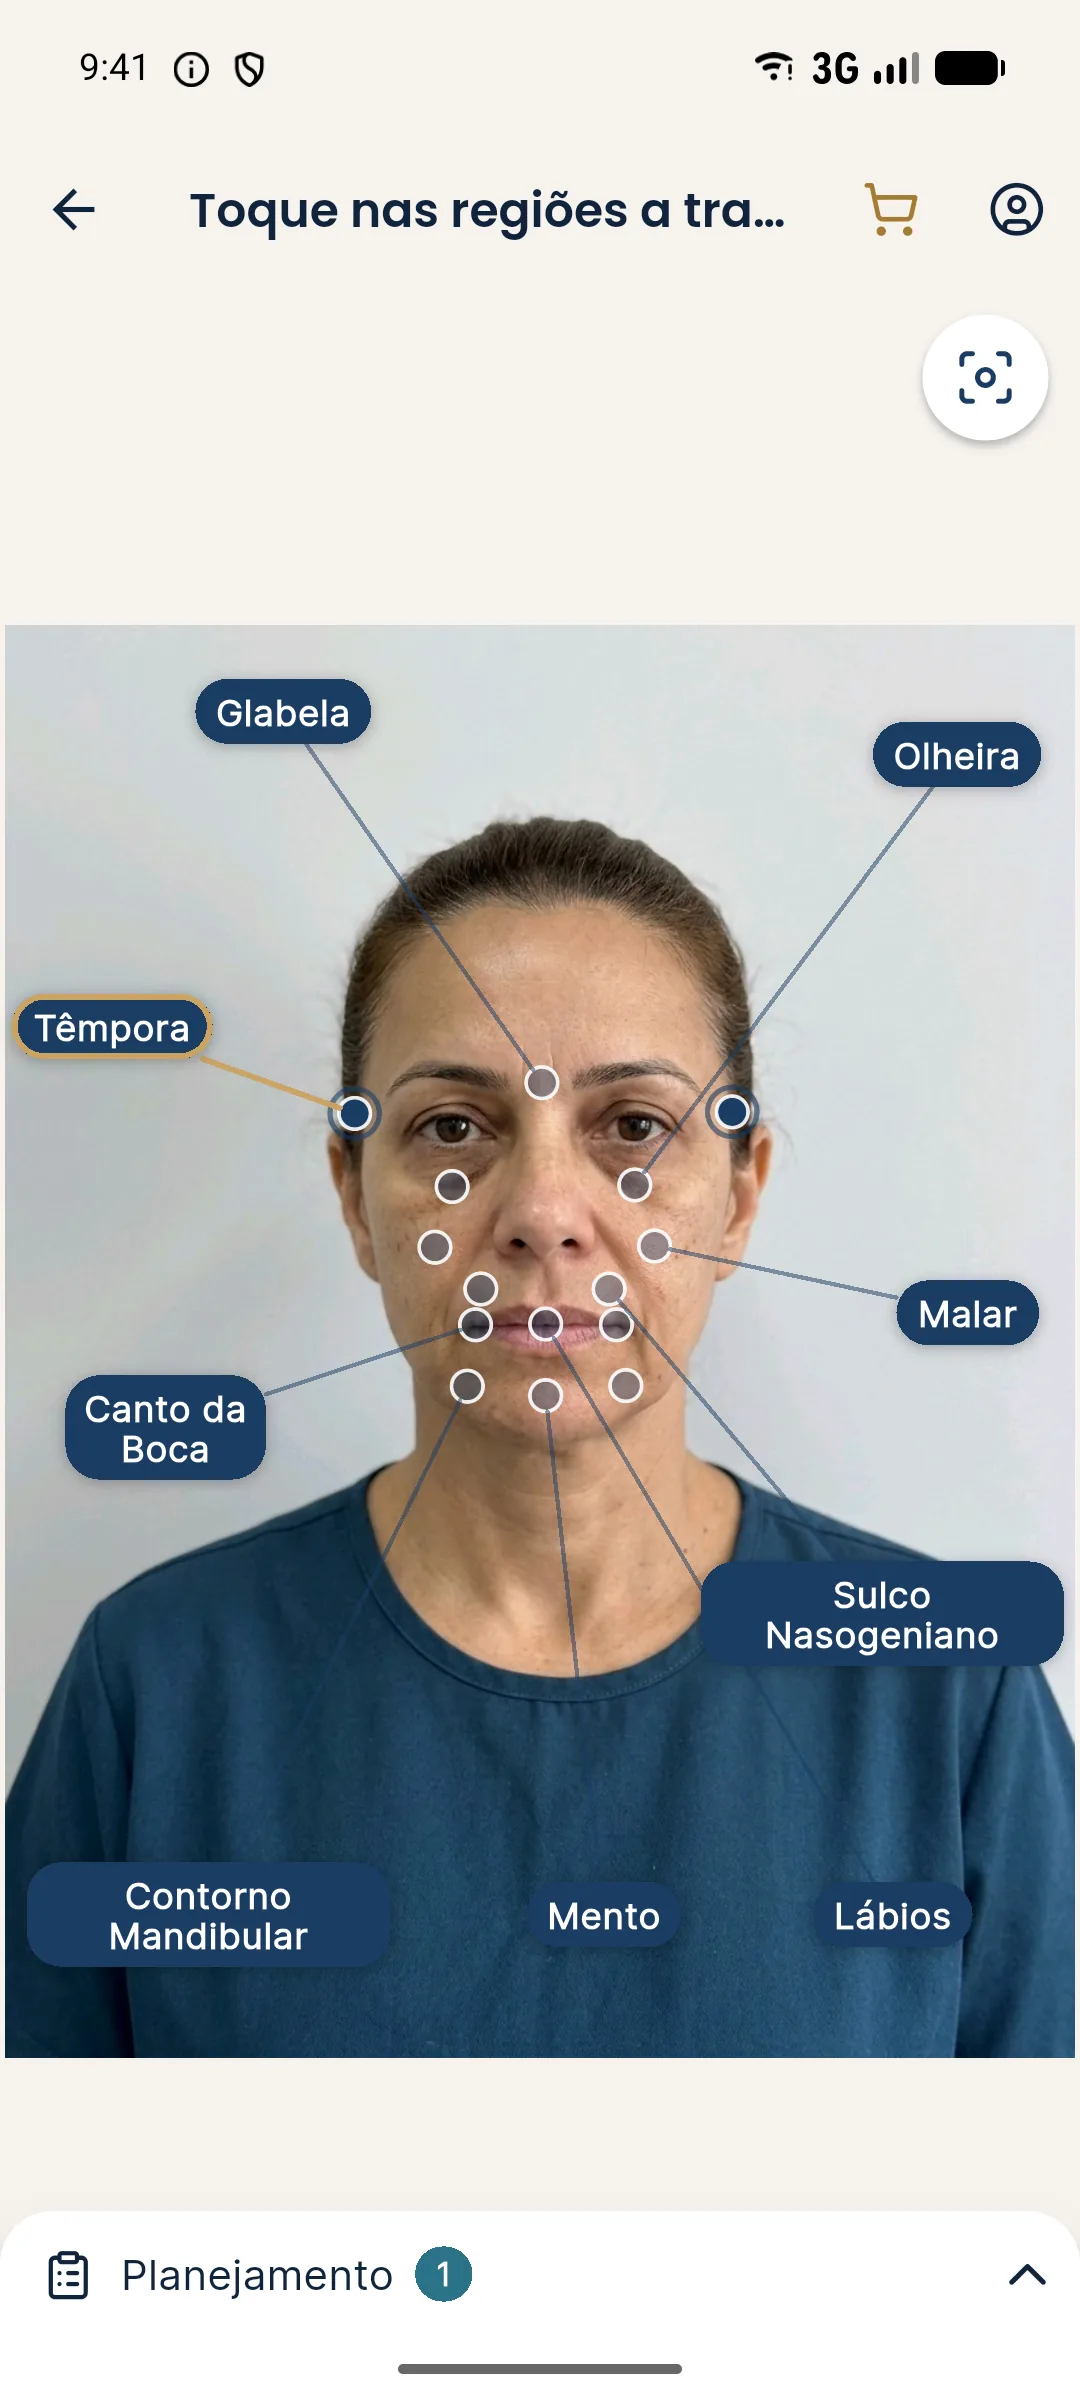
Here the limitation is central: the projection changes the volume of the temple, but it does not simulate eyebrow position or muscle action. If the patient expects to see the eyebrow "rise" in the image, explain that this is not what the tool does. The value of the simulation lies in showing that a gently softened lateral concavity can improve the harmony of the upper third, and nothing more.
See also limits of the 2D simulation and explaining that a simulation is not a guarantee.
How do you organize the plan in stages?
A common structure starts by assessing, then treating the most likely cause and only then refining. This avoids the trap of treating everything near the eye on the same day.
The cadence of follow-ups can follow reassessment at 3, 6 and 12 months.
What should you tell the patient?
The line corrects a common expectation without discouraging the patient. If they bring a reference photo of a high, arched eyebrow, return to their own facial identity; see facial identity: how to preserve it.
Assessment check
Quick review
Summary
A concave temple can weigh on the eyebrow tail and darken the corner of the eye, but not every heavy gaze comes from there. Separate the causes, treat the most likely one with conservative volume, reassess, and use the simulation as support for conversation, remembering that it does not simulate eyebrow position. Vascular safety and clear consent come before any decision.
Frequently asked questions
Does filling the temple lift the eyebrow?
It can help support the lateral area and reduce the feeling of heaviness, but the effect varies and does not replace assessing the eyebrow position. It is not a lift.
Toxin or filler for a heavy gaze?
It depends on the cause. When the heaviness comes from muscle action, toxin enters the reasoning. When it comes from lateral volume loss, filler may enter. Often the two are considered in stages.
What is the biggest risk in the temple?
The vascular one. There are important vessels in the temporal fossa, so the plan requires reviewed anatomy, conservative volume and hyaluronidase on hand in the case of hyaluronic acid.
Does Harmy show the eyebrow lifting?
No. The projection changes only the volume of the marked area and does not simulate eyebrow position or muscle action. Use the image as support for conversation.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.