
Facial Harmonization Plan for Patients From Another City or State

Quick facts
- Topic
- Facial harmonization plan for a patient who lives far away
- Main challenge
- Reassessment and complications outside immediate reach
- Usual strategy
- Few sessions, well spaced, with a follow-up script
- Critical point
- Agree in advance on who handles it if something happens
- Records
- Standardized photos, patient record, and a written plan in two copies
Treating someone who comes from far away changes planning more than it seems. It is not just logistics: distance affects the possibility of reassessment, the wait for a touch-up, and above all the handling of a complication. This page organizes the facial harmonization plan for this patient, focused on safety, predictability, and a follow-up that works outside the office.
What changes when the patient lives far away?
Three things. The first is reassessment: the two- or three-week follow-up, so useful for adjusting volume, stops being simple. The second is complications: persistent swelling, an asymmetry, or a vascular warning sign will not wait for the next trip. The third is the pressure to resolve everything at once, both from the patient (who paid for the trip) and from the professional's schedule.
The answer is to design the plan for distance from the first contact, rather than adapting it midway. This applies especially to the patient's first time, described in plan for first-time facial harmonization patients.
How do you organize the first contact at a distance?
The initial conversation can happen by message or video, to understand the concern, the history, and the expectations. It organizes the visit, but does not replace the exam. Ask for standardized photos before the trip to form a first impression, without making a clinical decision from them. The standardization rules are in standardized clinical photography.
Remote care has its own rules, which vary by professional council and change over time. Check what your council allows and read telemedicine and facial harmonization as a starting point, without taking it as a substitute for the official rule. If you use video for screening, tell the patient that the decision to treat only happens after an in-person exam.
How does the simulation help someone deciding from a distance?
The simulation helps the patient understand the plan before and after the trip. In Harmy, you create the projection at the consultation and can send the patient link: instead of an image, the patient opens a slider on their phone with the clinic's logo and contact, and reviews the idea calmly at home. This reduces impulse decisions in the room and leaves time for questions.
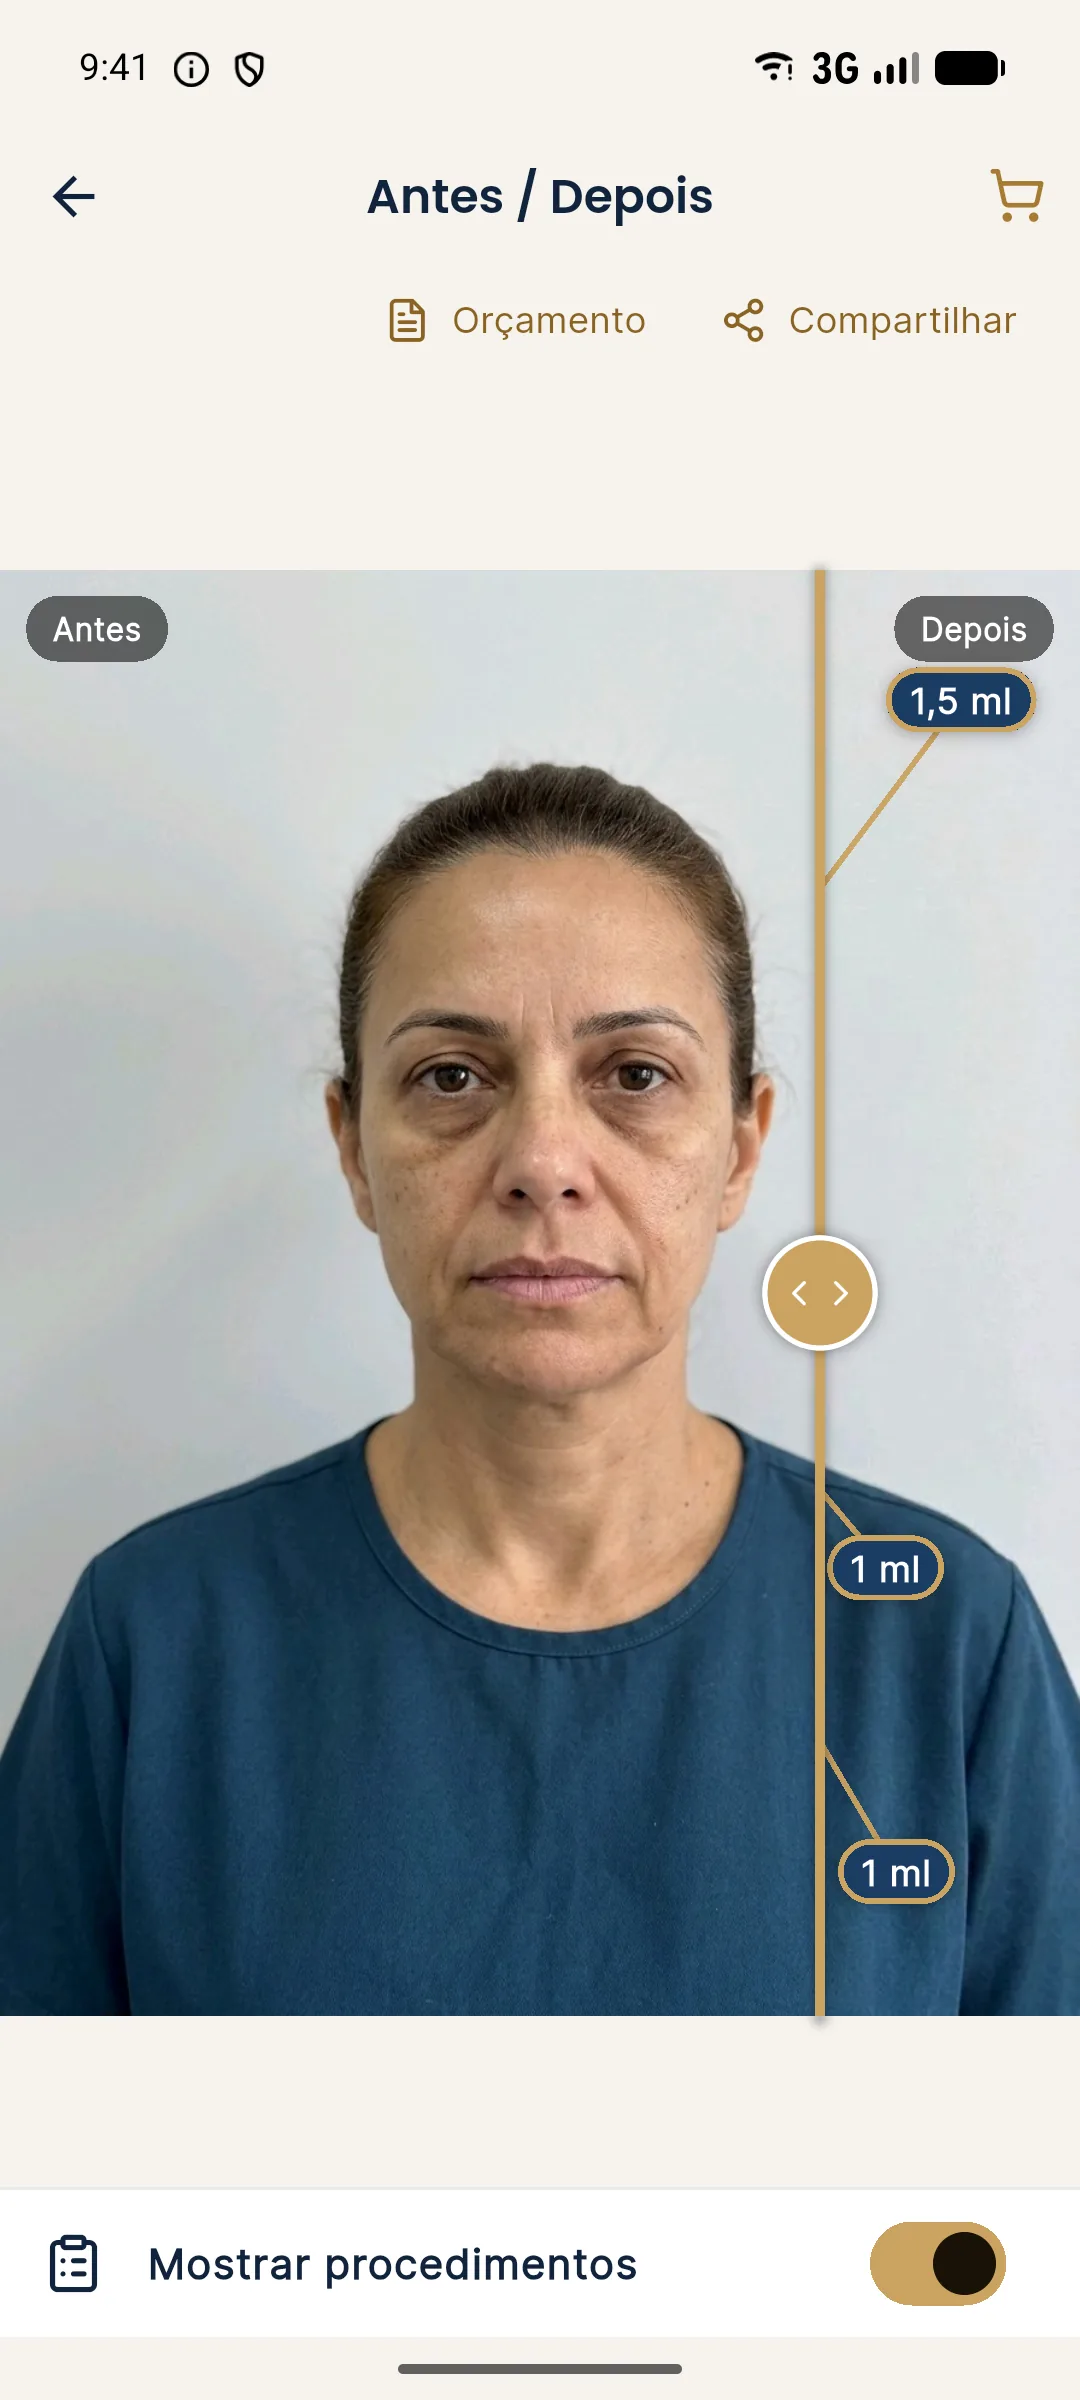
Remind the patient in writing that this is an illustrative simulation, not a promise of results. The conversation is covered in explaining that a simulation is not a guarantee, and the patient link appears in presenting the treated area with a magnifier.
How many areas should you treat per visit?
There is no magic number, and the decision rests with the professional. A useful idea is to limit the number of areas per visit to what you could follow from afar if something went wrong. Areas of higher vascular risk or more pronounced swelling, such as temples, under-eyes, and lips, call for more caution when follow-up is difficult.
The logic of ordering by risk is in prioritizing by risk in the plan and how many areas to treat per day. When the plan needs more than one stage, consider when to split the volume across sessions.
| Situation | Usual approach to consider |
|---|---|
| First time, few areas | Single session with low volume, then photo follow-up |
| Plan with several areas | Two or more visits, with the highest-risk one on a day when follow-up is possible |
| Area with pronounced swelling | Avoid treating on the final days of the patient's stay |
| Follow-up impossible | Shorter plan and detailed instructions |
Who handles a complication?
This is the most important question in the plan. Before the injection, agree in writing on what the patient should do for each sign: what is expected (mild swelling and bruising), what merits contact (asymmetry, nodule, worsening pain), and what is an emergency (severe pain, pallor or discoloration of the skin, vision changes). For the last category, the patient should go to a local emergency service and notify you immediately. See safety and complications: overview and vascular danger zones of the face.
Whenever hyaluronic acid is used, hyaluronidase must be available at the place of treatment. This matters even more when the patient leaves the next day. For the dialogue, see communicating the need for hyaluronidase.
How do you follow the result without an in-person follow-up?
Remote follow-up works best with agreed dates and photos in the same framing as the initial one. Define how many photos, on which days, and through which channel. Avoid assessing the result while swelling is still present, for reasons that appear in swelling gets in the way of comparing results. Agree with the patient on when to photograph, in when to photograph the result after the procedure.
The dates are suggestions for organizing, and it is up to the professional to adjust them to the procedure and the patient.
How do you organize documentation and payment?
Two copies of the written plan, one for the patient and one in the patient record, with a date and validity. The quote should say what it covers (treatment, touch-up, reassessment) and what it does not (travel, a second visit). In Harmy, the PDF quote comes out with the clinic's logo and contact, the price per ml of each area, validity, and informational installments. Details in linking the plan and the quote in facial harmonization and patient records and documentation in facial harmonization.
The touch-up policy should be clear: whether a touch-up is included, within what period, and who bears the travel cost. This avoids friction that arises when the patient needs to come back.
Reasoning test
Summary
For a patient from another city, the plan is smaller, better documented, and more thoroughly agreed upon. Define in advance who handles a complication, limit the areas per visit, use standardized photos and the patient link to support the decision, and keep an in-person follow-up always possible.
Frequently asked questions
Can I concentrate several areas in a single visit for an out-of-town patient?
It can be considered, but it is not the rule. The risk is stacking swelling, bruising, and rushed decisions. In general, it is better to limit the number of areas and split into spaced visits when the clinic allows.
How do I follow the result remotely?
Through standardized photos sent on agreed dates, in the same framing as the initial photo. Reading results from photos has limits, and an in-person visit should be possible when there is clinical doubt.
What if the patient has a complication in their own city?
This needs to be agreed in advance. The patient should leave with written instructions, warning signs, and a contact channel, and should know whom to see locally.
Is it safe to do the initial assessment by video?
Remote screening can organize the conversation, but it does not replace the in-person exam, and the professional council's rules on remote care should be checked. The decision to inject requires an in-person assessment.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.