
Flat Nose at the Base: Assessing the Dorsum and Projection
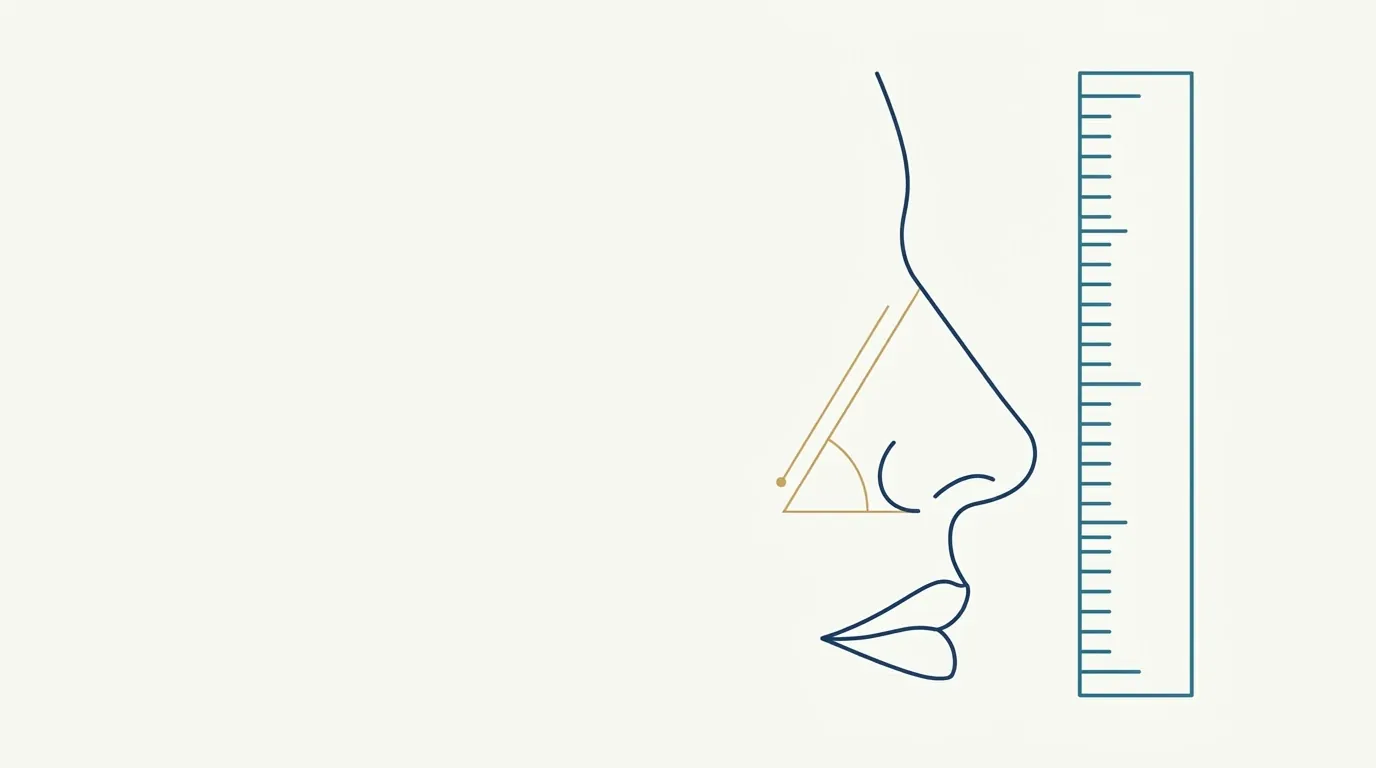
- Highlighted area
Quick facts
- Concern
- Nose that looks low and flat at the root or base, with little definition of the dorsum
- Key question
- Is the flatness in the dorsum and root of the nose, or is the midface underprojected and making the nose look low?
- Plan risk
- Raising the dorsum with product without assessing the midface, creating a tall, disproportionate nose
- First step
- Profile photo in the Frankfurt plane and measurement of the nasofrontal and nasolabial angles
"My nose is flat." The concern mixes different perceptions: a low dorsum, a deep root, little definition of the tip, or a flat face in which the nose seems sunken. What the patient sees from the front is almost never what matters for the decision. The person assessing needs to look in profile, measure and compare with the rest of the face.
This page shows how to separate what is dorsum and root from what is midface projection, and why the nose is an area where caution comes before volume. For an overview, see nose and nose anatomy for injectables.
What does "flat at the base" mean?
In practice, the patient uses the expression to describe at least four situations:
| Situation | What is observed | Supporting question |
|---|---|---|
| Low root | Deep point between the eyes, open nasofrontal angle | Where is the nasion relative to the eyelid? |
| Low dorsum | Poorly defined bridge, nose too "straight" in profile | Is the height bony or soft tissue? |
| Flat midface | Cheekbone and maxilla underprojected, nose looks sunken | Is the face as a whole flat? |
| Underprojected tip | Low tip, nasolabial angle closed or very open | Is the tip low or is the lip very projected? |
The profile exam is indispensable. From the front, a flat nose looks wide and short, but the cause only shows when projection is measured.
The role of bone and cartilage
The upper part of the nose is bony, formed by the nasal bone, and the lower part is cartilaginous, supported by the nasal cartilages. When the bone is short or the root is low, the dorsum looks flat, and no amount of soft tissue volume changes the structure underneath. When the cartilage has little support, the tip looks drooping.
The piriform aperture and the premaxilla define the base of the nose. A recession in these structures makes the base of the nose look flat, and the approach comes to involve assessing the midface and, sometimes, dentistry. See profile without midface projection.
Respect identity and the trait of origin
A low dorsum and a root with little projection are common traits in many ancestries, and they are not a defect. The proposal to "lift" the nose can take away the face's identity, and the patient may not notice until the result. Before planning, talk about what the person finds beautiful in her own nose and what really bothers her. See respecting traits of origin in the HOF plan.
What harmonization can do
The role of orofacial harmonization (HOF) in the nose is limited and should be approached with caution. In selected cases, the professional can discuss small contour changes to the dorsum with hyaluronic acid. The more frequent alternative is to treat what is around it: the midface, the upper lip and the chin, which change how the nose relates to the rest of the face.
- Midface: restoring or creating projection in the cheekbone and paranasal area can change the perception of the nose's depth. See cheekbone filler and flat cheekbones.
- Upper lip and philtrum: the relationship between the lip and the base of the nose influences how the nasolabial angle reads.
- Chin: a recessed chin makes the nose look larger, and the opposite also holds. See small chin.
- Dorsum and root: requires specific technique, anatomical knowledge and detailed consent, with high vascular risk.
When the problem is surgical
When the flatness comes from a short nasal bone, a very low root or insufficient cartilage, the definitive correction is surgical. Tell the patient plainly. An honest conversation about limits keeps them from going through several volume procedures trying to reach something only surgery offers. See concerns HOF does not solve and explaining nonsurgical rhinoplasty to the patient.
How to organize the plan
A prudent sequence usually follows this logic:
- Define whether the concern is about the nose, facial projection or both.
- Treat first what is around it and lower risk, if indicated, and reassess the profile.
- Only then discuss any intervention in the nose itself, if it still makes sense to the patient.
- Record standardized profile photos at each stage.
The order matters because changes to the cheekbone and lip often alter the perception of the nose. Many concerns diminish without having to touch the highest-risk area. See nose and upper lip: combining in the plan and nose and chin: combining in the plan.
Simulation and expectations
Harmy has no marking point for the nose and does not simulate changes to the dorsum or projection. The projection uses only the front photo, which does not show the profile. If useful, simulate the cheekbone or the lip to show the patient how neighboring areas change how the face reads, making clear that the nose stays as it is in the image.
Frequent mistakes
The first mistake is deciding from the front photo. From the front, almost every nose looks flat. Without the profile, the proposal is blind. The second mistake is raising the dorsum with product in someone with a flat midface: the nose ends up tall and the face even flatter. The third mistake is ignoring the trait of origin and proposing a nose from a different standard, leaving the patient with a face that is not theirs.
Summary for the decision
A flat nose at the base is a concern that calls for profile, measurement and a reading of the whole. Separate root, dorsum, tip and midface, respect the trait of origin, recognize when the case is surgical, and remember that the nose is a high vascular risk area. In many cases, balance comes from treating what is around it, at lower risk. All at the discretion of the qualified professional, according to the rules of their professional council in Brazil, without promising results.
Frequently asked questions
Can a flat nose be lifted with filler alone?
In some selected cases, volume can change how the dorsum reads, at the professional's discretion and after a profile assessment. The area carries a high vascular risk and the effect is limited when the cause is bony.
Can a flat nose be a lack of facial projection?
Yes. When the midface and maxilla have little projection, the nose looks low even if its size is normal. In those cases, assessing the cheekbone and premaxilla is part of the plan.
Is a flat nose different in each ancestry?
Yes. Dorsum, root and width vary among populations and are part of facial identity. The plan should respect the trait of origin instead of trying to fit the nose to a single standard.
Does Harmy simulate the nose?
No. Harmy has no marking point for the nose and uses only the front photo. It can simulate neighboring areas, such as the cheekbone, to talk about projection balance.
Harmy images are illustrative simulations generated by AI from the patient's photo to support the conversation between practitioner and patient. They are not a promise of results. Indication, technique, product and volume are solely the decision of the licensed practitioner. This content is for information only and does not replace a clinical assessment.